Help to stop smoking

Tag: smoking

  • Relapse

    Relapse

    Quitting smoking is often a difficult break from a powerful addiction. However, the real test of resilience often begins after the initial withdrawal phase. A relapse is not a failure, but a common obstacle—a sign that the addiction pathways in the brain are still active. To remain abstinent in the long term, you must not only stay away from smoking, but actively build a life in which smoking no longer plays a role. This transition requires practical strategies and an unwavering commitment.

    Identifying the Enemy: High-Risk Triggers

    The majority of relapses occur in predictable situations that act as powerful psychological cues. Understanding these personal triggers is the first line of defense. They fall broadly into four categories:

    1. Social Triggers: Being around other smokers is perhaps the most immediate danger. Attending a party where everyone steps outside for a smoke break or going to a bar where smoking is allowed can easily compromise resolve.
    2. Emotional Triggers: Stress, anxiety, boredom, anger, sadness, or even a celebration can all signal the brain that it needs the soothing or stimulating effect of nicotine. For example, the former smoker who always reached for a cigarette after a heated argument with a spouse must have a replacement plan ready before the next disagreement even begins.
    3. Routine Triggers: These are the habitual pairings—the ritualistic moments in the day tied to a cigarette. The first cup of coffee in the morning, the end of a meal, or getting into the car are all prime examples. These triggers are the most ingrained and require consistent, active substitution.
    4. Craving and other nicotine withdrawal symptoms: a very strong urge to smoke (craving), being in a bad mood (sad or depressed, angry, irritable, impatient or agitated, anxious or nervous, rapid mood swings), poor sleep (insomnia), difficulty concentrating, increased hunger and weight gain. But quitting smoking also brings about a rapid improvement in smell and taste. These symptoms are alleviated by nicotine replacement therapy.

    The Escape Plan: Avoidance and Substitution

    To successfully navigate these high-risk moments, preparation is key. Avoidance is the simplest tactic for the immediate term. For instance, if a specific coffee shop was the regular smoking spot, the former smoker should temporarily change their morning routine, perhaps opting for tea at home or taking a different route to work.

    When avoidance is impossible, substitution becomes the main tool. This is where the commitment to a new behavior must override the old habit. If stress is the trigger, a five-minute substitution could involve deep-breathing exercises, a quick walk around the block, or texting a supportive friend. If the trigger is the end of a meal, the former smoker needs to immediately engage the mouth and hands with something else—brushing teeth right away, chewing nicotine gum, or eating a piece of hard candy. The crucial action is disrupting the old routine instantly.

    Navigating Cravings: The Four D’s

    Cravings, even months after quitting, are intense but short-lived. They typically peak within three to five minutes. Former smokers need a repertoire of rapid response mechanisms to survive this brief window of desire. In addition to taking a nicotine gum of lozenge, experts recommend the “Four D’s” strategy:

    • Delay: Wait it out. Tell oneself, “I will wait five minutes and see how I feel then.” By delaying, the intensity often subsides before the person gives in.
    • Deep Breathe: Take ten slow, deep breaths. This not only distracts but also helps manage the anxiety often associated with the craving.
    • Drink Water: Sip a glass of water slowly. The physical act engages the mouth and provides a minor distraction.
    • Do Something Else: Immediately change activities. If one is sitting, they should stand up and move. If they are talking, they should shift the topic. A quick distraction breaks the mental focus on the craving.

    Weight Gain

    Many former smokers gain a few pounds after quitting smoking. Weight gain can be delayed by using nicotine replacement products (patches, gum, tablet). This way, you can tackle one difficulty at a time: first, you quit smoking, then you use nicotine replacement products for a few months, and only when you stop using these products will you possibly gain weight.

    The Relapse Management Protocol

    The ultimate mistake is to treat a single slip as a total failure. A single cigarette is a slip, not a surrender. The danger lies in the self-defeating mindset that follows, leading to the full return to regular smoking.

    A successful relapse management protocol requires compassion and immediate action. If a former smoker has a cigarette, the focus must be on what happened just before that moment, identifying the trigger (Was it alcohol? Stress? A specific person?) and analyzing what defensive measure was skipped. The goal is to learn from the mistake and immediately recommit to the quit effort, disposing of any remaining cigarettes and reinforcing the substitution tactics for the next high-risk situation.

    Long-term success is built on the realization that abstinence is a continuous, conscious effort. It requires maintaining motivation, celebrating every smoke-free day, and understanding that managing the urge to smoke is a skill that improves, but never entirely disappears. Staying vigilant against the triggers is the true path to a permanently smoke-free life.


    Use the ‘Comments’ field below to share your experience or to suggest improvements to this article.



  • Quitting smoking

    Quitting smoking

    Everything you need to know to stop smoking for good:
    – 10 rules to stop smoking,
    – post cessation weight gain,
    – addiction and withdrawal symptoms,
    – effective methods and treatments,
    – avoiding relapse,
    – the health benefits of quitting smoking
    – Addresses of helplines, doctors and clinics, and discussion forums


  • Community

    Community

    Do not quit alone, the support from others is crucial. In this section:

  • Nicotine addiction

    Nicotine addiction

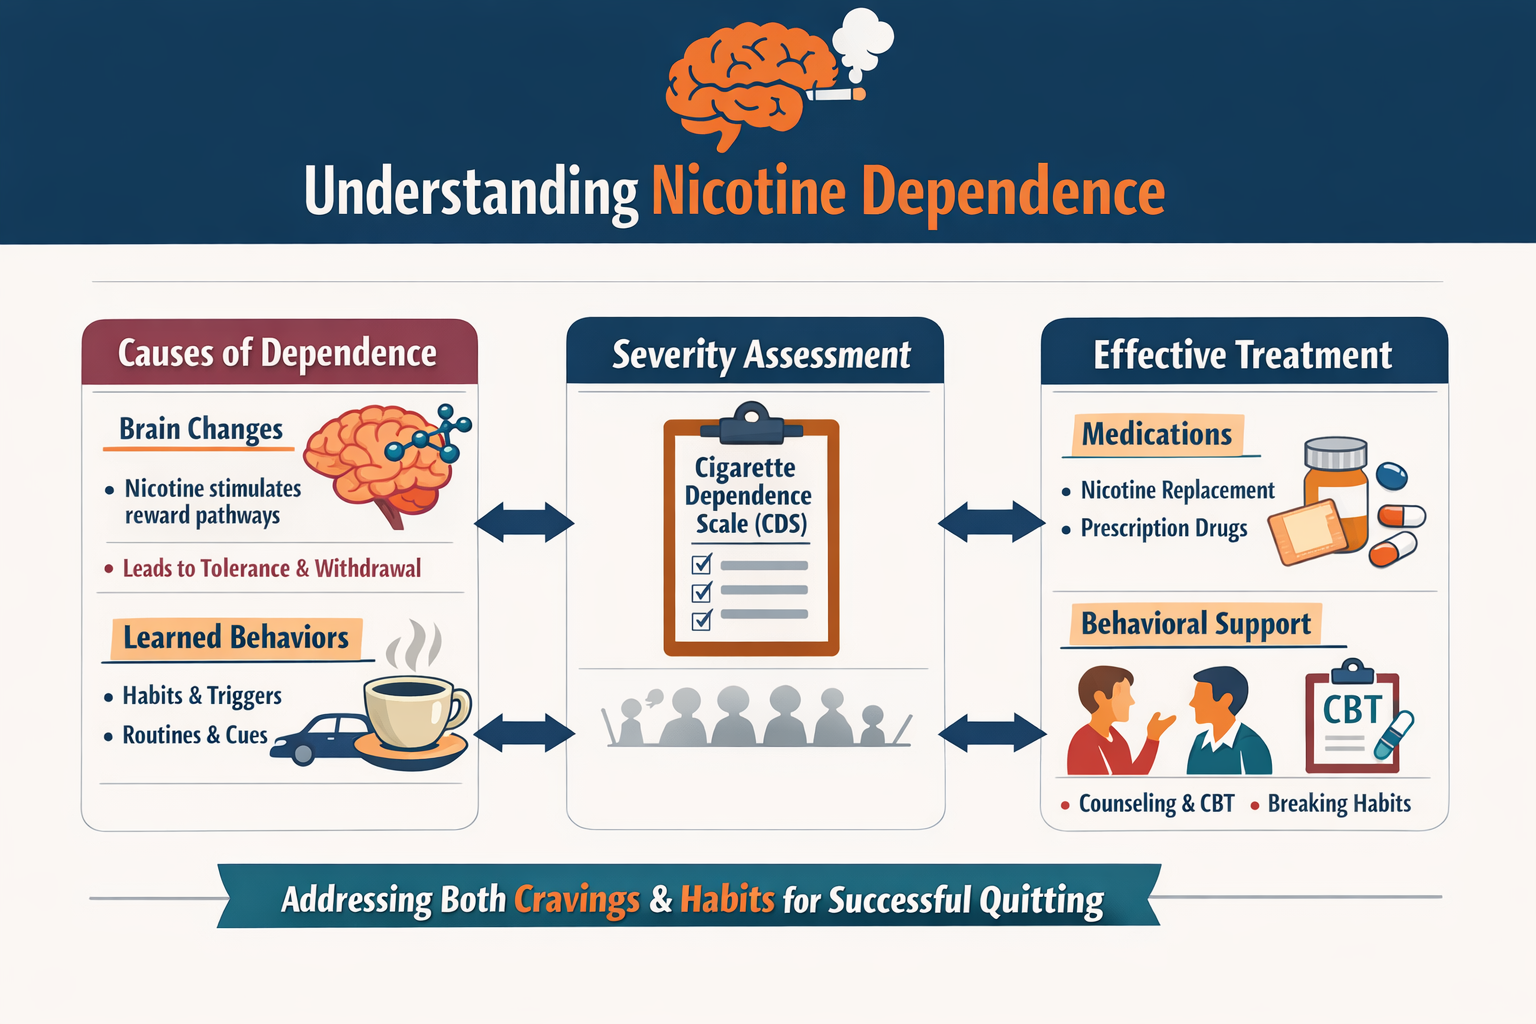
    Nicotine addiction is a loss of control over tobacco use driven by both brain changes and learned behaviors. Nicotine stimulates brain reward pathways, causing craving, withdrawal, and compulsive smoking, while routines and triggers reinforce the habit. Dependence severity can be measured with tools like the Cigarette Dependence Scale. The most effective treatment combines medications (nicotine replacement or prescription drugs) with behavioral support to address both physical cravings and psychological habits.

    Definition and Symptoms

    At its core, nicotine dependence is a loss of control over nicotine or tobacco use, it is a state where the body and mind have adapted to the presence of nicotine, the primary addictive chemical in tobacco. When nicotine is withheld, a cluster of uncomfortable withdrawal symptoms emerges.

    The symptoms of nicotine addiction can manifest in various ways, combining physical and psychological distress. Key indicators include:

    • Loss of Control: Continuing to smoke despite the awareness of serious health issues, like lung or heart disease, caused by smoking, and despite the social consequences.
    • Compulsive Use: Consumption despite the desire to quit. Repeated and unsuccessful attempts to quit or reduce tobacco consumption.
    • Social Avoidance: Giving up activities or avoiding places where smoking is prohibited because of the inability to abstain.
    • Withdrawal Symptoms: Experiencing symptoms upon cessation, such as intense cravings, irritability, anxiety, restlessness, difficulty concentrating, depressed mood, insomnia, increased hunger, weight gain and insomnia.
    • Tolerance: The disappearance of side effects (e.g. nausea) experienced by new users, a reduced effect at a given dose, and the need to consume more to alleviate cravings and withdrawal symptoms. This is especially true for new smokers, because regular smokers usually smoke the same amount over many years.
    • Early Morning Smoking: Lighting up a cigarette within the first 30 minutes of waking. The shorter the time to the first cigarette, the higher the degree of dependence.

    Assessing the Degree of Dependence

    While a clinical diagnosis of nicotine dependence is based on criteria established by psychiatric manuals, researchers and clinicians also employ self-report tests to measure its severity.

    One such instrument, designed to provide a continuous and nuanced index of a smoker’s dependence, is the Cigarette Dependence Scale (CDS), developed by the author of this website and his colleagues. The shorter, 5-item version provides a quick test that can be used to tailor treatment. The longer, 12-item version (CDS-12) assessesmultiple facets of the dependence construct. By having the smoker rate statements on a five-point scale, the questionnaire provides a total score that clinicians can use to gauge the severity of the addiction, select the most appropriate treatment approach, and monitor the patient’s progress during cessation efforts.

    The Biological Mechanism: Nicotine and the Brain

    The invisible chain of addiction is forged in the brain’s complex circuitry. Nicotine acts as a powerful psychoactive agent, mimicking the natural neurotransmitter acetylcholine.

    Upon inhalation, nicotine reaches the brain in mere seconds. There, it binds to specific protein channels, known as nicotinic acetylcholine receptors (nAChRs), located throughout the brain. When nicotine binds to these receptors, it triggers the release of several neurochemicals, most notably dopamine in the brain’s reward centers. This rush of dopamine produces the transient feelings of pleasure, focus, and reward that reinforce the act of smoking. The brain is somehow tricked to associate smoking with other rewards that are essential for survival.

    With repeated exposure, the brain adapts: it produces an excess number of nAChRs in an attempt to compensate for the constant stimulation—a process called upregulation. This adaptation is the biological basis for tolerance, meaning the smoker needs more nicotine to achieve the same effect. When the nicotine supply is cut off, these upregulated receptors are left craving stimulation, leading to intense withdrawal symptoms and driving the compulsive need to smoke again. This cycle of seeking relief from discomfort is known as negative reinforcement, cementing the addiction.

    The key factor is that the addictiveness of a nicotine delivery device depends on the speed at which nicotine is delivered to the blood and brain. Cigarettes have the fastest nicotine delivery, as a large amount of nicotine reaches the brain within seconds of inhaling a puff. In contrast, nicotine patches, gum, lozenges, and pouches deliver the nicotine dose much more slowly, so these products are not addictive. Electronic cigarettes and heated tobacco products have a medium delivery rate, nd some of these products can also be addictive depending on the amount and speed of nicotine delivery.

    The Behavioral Component: Triggers and Rituals

    Cigarette addiction is not purely chemical; it is also deeply interwoven with learned behaviors and environmental cues. This is the behavioral component of the dependence.

    Smokers repeatedly link the physical act of smoking with daily routines, emotional states, and social settings. The morning coffee, the work break, driving a car, finishing a meal, talking on the phone, or experiencing stress or anxiety all become powerful cues, or “triggers,” that signal the need for a cigarette. The mere sight or smell of tobacco, or being in the presence of other smokers, can elicit a powerful craving. These ritualistic associations create a psychological dependence that must be addressed alongside the physical addiction to ensure long-term cessation.

    Treatment Methods

    The treatment for cigarette addiction is most effective when it is multi-faceted, addressing both the biological craving and the deeply ingrained behavioral habits, and when it combines pharmacological with behavioral treatments.

    Pharmacological Treatments aim to manage the physical symptoms of withdrawal and reduce the reinforcing effects of nicotine:30

    • Nicotine Replacement Therapy (NRT): Available as patches, gum, lozenges, inhalers, and sprays, NRT delivers controlled doses of nicotine without the harmful toxins of tobacco smoke, and at a slower rate than cigarettes, making these products non-addictive. This helps mitigate withdrawal symptoms. Combining a long-acting form (like the patch) with a short-acting form (like the gum) for acute cravings is more effective than using either product alone.
    • Prescription Medications: Drugs like varenicline, cytisine and bupropion are non-nicotine options. Varenicline and cytisine work by partially stimulating the nAChR, reducing both cravings and the pleasure derived from smoking, while bupropion, originally an antidepressant, is thought to influence dopamine and norepinephrine levels to alleviate withdrawal.

    Although these are not medical treatments, you can also obtain nicotine from electronic cigarettes or nicotine pouches if you do not wish to use the medications mentioned above.

    Behavioral Treatments focus on disrupting the psychological and learned components of the addiction:

    • Cognitive Behavioral Therapy (CBT): This approach helps the smoker identify their triggers and develop effective coping strategies and relapse prevention skills. It reframes the person’s thoughts and behaviors related to smoking.
    • Counseling and Support: Individual or group counseling, often delivered by specialists or through telephone quitlines, provides essential support, motivation, and practical guidance on navigating the challenges of quitting.
    • Motivational Interviewing (MI) is a specific technique used to help ambivalent smokers explore and resolve their feelings about cessation.

    Successful smoking cessation is based on a combination of medication and behavioral support tailored to your individual needs and level of dependence. Millions of people have successfully quit smoking with the help of pharmacological and behavioral aids, and you can do it too, just like them, and improve your health immediately.


    Use the ‘Comments’ field below to share your experience or to suggest imporovements to this article.


    References:

    Etter, JF., Le Houezec, J. & Perneger, T. A Self-Administered Questionnaire to Measure Dependence on Cigarettes: The Cigarette Dependence Scale. Neuropsychopharmacol 28, 359–370 (2003). https://doi.org/10.1038/sj.npp.1300030

    Jean-François Etter, Comparing the validity of the Cigarette Dependence Scale and the Fagerström Test for Nicotine Dependence, Drug and Alcohol Dependence, Volume 95, Issues 1–2, 2008, Pages 152-159, ISSN 0376-8716, https://doi.org/10.1016/j.drugalcdep.2008.01.017.

    Jean-François Etter, A comparison of the content-, construct- and predictive validity of the cigarette dependence scale and the Fagerström test for nicotine dependence, Drug and Alcohol Dependence, Volume 77, Issue 3, 2005, Pages 259-268, ISSN 0376-8716, https://doi.org/10.1016/j.drugalcdep.2004.08.015.