Help to stop smoking

Tag: nicotine

  • Diabetes and smoking

    Diabetes and smoking

    Smoking increases the risk of developing type 2 diabetes. For people who already have diabetes, smoking makes the condition harder to manage and increases the risk of serious complications. However, quitting smoking can make a real difference to both the prevention and management of the disease.

    Does smoking increase the risk of diabetes?

    Yes, research has established that cigarette smoking increases the risk of developing type 2 diabetes. People who smoke are approximately 30–40% more likely to develop the disease than non-smokers. The risk also increases with the number of cigarettes smoked. Even passive smoking is associated with an increased risk of type 2 diabetes.

    The main reason is the chemicals in cigarette smoke, which interferes with the way the body uses insulin. Insulin is a hormone produced by the pancreas that allows glucose (sugar) to move from the blood into the body’s cells, where it is used for energy. When cells become less responsive to insulin, a condition known as insulin resistance develops. Blood sugar levels rise, and the pancreas has to work harder to produce enough insulin.

    The chemicals in cigarette smoke cause inflammation and damage to cells, interfering with the body’s ability to regulate blood sugar. Smoking is also associated with increased abdominal fat, another risk factor for type 2 diabetes.

    The link is not limited to heavy smokers. Even people who smoke relatively few cigarettes have an increased risk.

    Why is smoking particularly dangerous for people who have diabetes?

    Having diabetes already increases the risk of cardiovascular disease, kidney problems, nerve damage and vision loss. Smoking adds to these risks, making the combination particularly harmful.

    One important problem is blood sugar control. The chemicals in cigarette smoke raise blood sugar and make the body less sensitive to insulin. As a result, smokers with diabetes may need more insulin or other medication to keep their glucose levels under control.

    Smoking also damages blood vessels and reduces circulation. This is especially concerning in people with diabetes, who are already more vulnerable to damage to their arteries and small blood vessels.

    The combination of diabetes and smoking substantially increases the risk of heart attack and stroke. It also increases the likelihood of kidney disease and damage to the blood vessels in the eyes, which can eventually lead to blindness.

    Poor circulation is particularly dangerous in the legs and feet. People with diabetes may already have reduced sensation because of nerve damage. When smoking further reduces blood flow, even a small wound or blister can become difficult to heal. Infections and foot ulcers may develop, sometimes leading to amputation.

    Smoking can also worsen diabetic neuropathy, a condition involving damage to the nerves that can cause pain, tingling and numbness, particularly in the feet and legs.

    In short, smoking makes an already serious disease considerably more dangerous.

    What happens when someone with diabetes quits smoking?

    Quitting smoking is one of the most important steps a person with diabetes can take to protect their health. The benefits begin soon after the last cigarette, even in people who have smoked for many years.

    When exposure to smoke stops, the body gradually becomes more responsive to insulin. Blood sugar levels may become easier to control, and some people find that their diabetes medication requirements change.

    Research has found that insulin can become more effective within approximately eight weeks of quitting smoking. Over time, stopping smoking also reduces the additional cardiovascular and vascular risks associated with tobacco use.

    Better circulation can help protect the feet and legs, while reducing the risk of heart disease, stroke and further damage to the kidneys and eyes.

    There is one important point to bear in mind. Some people gain weight after quitting smoking, which can temporarily affect blood sugar levels. The risk of developing type 2 diabetes may also remain elevated for a period after cessation, partly because of weight gain. However, research shows that this risk decreases with time since quitting. The long-term health benefits of stopping smoking are substantial.

    People with diabetes who quit should monitor their blood sugar regularly, particularly during the first weeks and months. Their doctor may need to review their medication or adjust their treatment as their glucose levels change.

    Quitting does not cure diabetes or reverse existing organ damage, but it can make the disease easier to manage and reduce the risk of further complications.


    Please use the Comments field below to share your experience or to suggest improvements to this article.


    Rate this article by clicking on the desired number of stars:
    (No Ratings Yet)


    References

    1. Centers for Disease Control and Prevention (CDC). Diabetes and Smoking. Read more.
    2. US Food and Drug Administration (FDA). How Smoking Can Increase Risk for and Affect Diabetes. Read more.
    3. Pan A, Wang Y, Talaei M, Hu FB, Wu T. Relation of active, passive, and quitting smoking with incident type 2 diabetes: a systematic review and meta-analysis. Lancet Diabetes Endocrinol. 2015 Dec;3(12):958-67. https://doi.org/10.1016/s2213-8587(15)00316-2


  • Allen Carr’s Easyway method

    Allen Carr’s Easyway method

    Allen Carr’s Easyway method is one of the best-known approaches to stopping smoking without medication or nicotine replacement products. Its central idea is quite different from conventional smoking cessation programmes: instead of teaching smokers to resist the urge to smoke, it aims to change the way they think about smoking so that they no longer feel the need to smoke. But does it work?

    What is the Easyway method ?

    The method was developed by Allen Carr, a former heavy smoker who quit in 1983. It is best known through his book The Easy Way to Stop Smoking, first published in 1985 and which has sold over 13 million copies, and through group seminars and online courses.

    The approach is based on the idea that smokers continue smoking largely because they believe cigarettes provide pleasure, relieve stress, help them concentrate or offer comfort. According to Carr, these perceived benefits are largely an illusion: smoking mainly relieves the discomfort caused by nicotine withdrawal, creating a cycle of dependence.

    During a seminar, participants are encouraged to question their beliefs about smoking and understand how nicotine addiction works. Rather than relying on willpower or seeing cigarettes as something they must give up, they are encouraged to view quitting as gaining freedom from an addiction. The method also aims to remove the fear of withdrawal, weight gain and life without cigarettes.

    Unlike most conventional programmes, Allen Carr’s method does not routinely use nicotine replacement therapy or medication. Participants are generally encouraged to continue smoking until the end of the session, when they are asked to smoke their last cigarette.

    Is there a scientific basis for the method?

    The method’s explanation of nicotine addiction has some similarities with established psychological concepts. In particular, questioning beliefs about smoking and changing the way a person responds to cravings are recognised elements of cognitive behavioural approaches.

    However, Allen Carr’s method was not developed on the basis of scientifically validated psychological principles, and many experts believe that some of its underlying assumptions are incorrect. For example, the idea that quitting can be entirely free of withdrawal symptoms is not consistent with what is known about nicotine addiction. Many smokers experience cravings, irritability, anxiety, sleep disturbances or difficulty concentrating after stopping.

    What do scientific studies show?

    Despite the method’s popularity, relatively few clinical studies have examined its effectiveness. A systematic review identified only six studies suitable for analysis, including two randomised controlled trials:

    A large British trial, involving 620 smokers, compared a 4 to 6 hour Easyway seminar with a specialist Stop Smoking Service offering behavioural support and nicotine replacement therapy. After six months, the quit rates were 19.4% and 14.8%, respectively. The difference was not statistically significant, meaning that the study could not establish that either approach was more effective.

    In an Irish trial, 300 smokers were randomly assigned to either a in-person, 5 hours single-session Easyway seminar or to the online National Smoking Cessation Service ‘Quit.ie’. The researchers found higher quit rates among participants attending the seminar than among those using the online service. After one year, 22% of the in-person seminar participants had stopped smoking, compared with 11% in the online comparison group.There is, however, one important difference between the two groups that makes them incomparable: a five-hour in-person session, regardless of its content, will inevitably have a greater impact than an online system, especially if participation rates in online activities are low, which was the case in this study.

    Evidence for the book alone is particularly limited. Reading it has not yet been shown convincingly to increase long-term quit rates.

    Should you try Allen Carr’s method?

    Allen Carr’s method emphasis on challenging the perceived benefits of cigarettes may be helpful for some smokers, but claims of exceptionally high success rates are unfounded. Scientific data indicate that the Easyway seminar is no more effective than other in-person methods. Furthermore, the fact that this method emphasizes avoiding nicotine replacement therapies may be counterproductive.

    Nicotine replacement therapy, prescription medications (varenicline, cytisine) in-persdon behavioural support and quitlines have a much larger body of scientific evidence behind them. There is no reason to avoid these treatments.


    Please use the Comments field below to share your experience or to suggest improvements to this article.


    Rate this article by clicking on the desired number of stars:
    (No Ratings Yet)


    References

    1. Possenti I, Scala M, Lugo A, Clancy L, Keogan S, Gallus S. The effectiveness of Allen Carr’s method for smoking cessation: A systematic review. Tob Prev Cessat. 2023 Sep 29;9:29. https://doi.org/10.18332/tpc/172314
    2. Keogan S, Li S, Clancy L. Allen Carr’s Easyway to Stop Smoking – A randomised clinical trial. Tobacco Control 2019;28:414-419. https://doi.org/10.1136/tobaccocontrol-2018-054243
    3. Frings D, Albery IP, Moss AC, et al. Comparison of Allen Carr’s Easyway programme with a specialist behavioural and pharmacological smoking cessation support service: a randomized controlled trial. Addiction. 2020;115(5):977–985. https://doi.org/10.1111/add.14897

  • Acupuncture to quit smoking

    Acupuncture to quit smoking

    Acupuncture is sometimes presented as a natural way to stop smoking, reduce nicotine cravings and ease withdrawal symptoms. It is particularly popular among people looking for an alternative to nicotine replacement products or medication. But does it actually help people quit smoking? What does the scientific evidence tell us?

    What is acupuncture?

    Acupuncture is a traditional Chinese practice in which very fine needles are inserted into specific points on the body. For smoking cessation, treatment often involves stimulating points around the ears, hands and other parts of the body. Some practitioners also use ear acupuncture (auricular acupuncture), in which needles are placed at specific points on the outer ear.

    The treatment is based on the idea that stimulating these points may influence the nervous system and help regulate certain bodily functions. In the context of smoking cessation, it is intended to reduce nicotine cravings, anxiety, irritability and other withdrawal symptoms.

    What does the scientific evidence say?

    Acupuncture has been studied in numerous clinical trials, but there is little convincing evidence that it helps smokers quit. A Cochrane review (which is an authoritative souce) that included 38 randomized clinical trials concluded that:

    The review did not find consistent evidence that active acupuncture or related techniques increased the number of people who could successfully quit smoking. However, some techniques may be better than doing nothing, at least in the short term, and there is not enough evidence to dismiss the possibility that they might have an effect greater than placebo

    In its 2024 smoking cessation guidelines, the World Health Organization (WHO) concluded that the evidence is currently insufficient to recommend acupuncture or acupressure for quitting tobacco.

    Should you try acupuncture to quit smoking?

    However, if you find that acupuncture helps you relax or can provide support during the quitting process, you may want to try it, but acupuncture should not be used as a substitute for treatments that have been proven effective for smoking cessation. Nicotine replacement therapy, medications such as varenicline and cytisine, and behavioural support have much stronger scientific evidence behind them.

    If you decide to try acupuncture, choose a qualified practitioner who uses sterile, single-use needles. Acupuncture is generally considered safe when performed by a properly trained professional, although minor bleeding, bruising or temporary soreness can occur.


    Please use the Comments field below to share your experience or to suggest improvements to this article.


    Rate this article by clicking on the desired number of stars:
    (No Ratings Yet)


    References:

    1. World Health Organization (2024). WHO clinical treatment guideline for tobacco cessation in adults. (https://www.who.int/publications/b/74755
    2. White AR, Rampes H, Liu JP, Stead LF, Campbell J. Acupuncture and related interventions for smoking cessation. Cochrane Database of Systematic Reviews 2014, Issue 1. Art. No.: CD000009. https://doi.org/10.1002/14651858.CD000009.pub4.

  • Smoking and Female Sexual Function

    Smoking and Female Sexual Function

    Smoking also affects sexual function. For women, smoking may affect sexual desire, arousal, vaginal lubrication and the ability to reach orgasm. These effects are not always recognised, yet they can have a significant impact on intimate relationships and quality of life.

    How does smoking affect female sexual function?

    Sexual arousal depends partly on good blood circulation. When a woman becomes sexually aroused, blood flow to the clitoris and surrounding genital tissues increases. This contributes to genital sensitivity, swelling and vaginal lubrication.

    Nicotine causes blood vessels to narrow, while the many toxic substances in cigarette smoke damage the blood vessels and interfere with normal circulation. Smoking may therefore reduce blood flow to the genital area, making physical arousal more difficult.

    Some women who smoke experience reduced genital sensitivity, difficulties becoming aroused or insufficient vaginal lubrication. This can make sexual intercourse uncomfortable and less enjoyable.

    Smoking may also affect sexual desire. Although the relationship between smoking and libido is complex, nicotine dependence, changes in mood, hormonal effects and smoking-related health problems may all contribute to a reduced interest in sex.

    Orgasm can also be affected. Because sexual response depends on the interaction between blood circulation, nerve function and genital sensitivity, smoking may make it more difficult for some women to reach orgasm or experience the same level of sexual pleasure.

    Not every woman who smokes will experience these problems, and sexual difficulties can have many other causes.

    What does scientific research show?

    Studies have found an association between smoking and female sexual dysfunction. A systematic review and meta-analysis published in 2022, involving more than 15,000 women, found that female smokers had approximately 48% higher odds of sexual dysfunction than non-smokers.

    Other research has suggested that the risk may increase with the amount and duration of smoking.

    Although these findings do not prove that smoking is directly responsible for every sexual difficulty, they provide further evidence that tobacco use can affect women’s sexual health.

    Can quitting smoking improve female sexual function?

    Quitting smoking may help improve sexual function by allowing blood circulation and cardiovascular health to recover.

    Encouragingly, a prospective study examined sexual function in premenopausal women who stopped smoking. After nine months of smoking cessation, the researchers found significant improvements in sexual function: the proportion of women classified as having sexual dysfunction fell from 86% to 35%.

    Improvements are not guaranteed, however. Sexual function is influenced by many factors, including age, hormonal changes, menopause, stress, relationship difficulties and certain medications. Some women may notice changes after quitting, while others may not experience a significant difference.

    Smoking, hormones, menopause and fertility

    Smoking can also affect female reproductive health. Research suggests that women who smoke tend to reach menopause earlier than non-smokers, sometimes by several years.

    Smoking is also associated with reduced fertility and other reproductive health problems. Stopping smoking is therefore particularly important for women who are planning a pregnancy or wish to protect their long-term reproductive health.

    This matters because declining oestrogen levels during menopause can lead to vaginal dryness, reduced vaginal elasticity and discomfort during sexual intercourse. These changes may affect sexual desire and satisfaction.

    Speak to your doctor

    If you continue to experience vaginal dryness, pain during sex, reduced sexual desire or difficulties with arousal or orgasm, speak to a healthcare professional. These problems are common and often treatable.


    Please use the Comments field below to share your experience or to suggest improvements to this article.


    Rate this article by clicking on the desired number of stars:
    (No Ratings Yet)


    References

    1. Salari N, Hasheminezhad R, Abdolmaleki A, Kiaei A, Shohaimi S, Akbari H, Nankali A, Mohammadi M. The effects of smoking on female sexual dysfunction: a systematic review and meta-analysis. Arch Womens Ment Health. 2022 Dec;25(6):1021-1027. https://doi.org/10.1007/s00737-022-01281-1.
    2. Harte CB, Meston CM. The inhibitory effects of nicotine on physiological sexual arousal in nonsmoking women: results from a randomized, double-blind, placebo-controlled, cross-over trial. J Sex Med. 2008 May;5(5):1184-1197. https://doi.org/10.1111/j.1743-6109.2008.00778.x
    3. Celikhisar H, Dasdemir Ilkhan G, Irer B. Effects of smoking cessation on sexual functions and health quality of life in premenopausal women: A prospective case – Controlled study. Int J Clin Pract. 2021 Mar;75(3):e13796. https://doi.org/10.1111/ijcp.13796
    4. Soheila Nazarpour, Masoumeh Simbar, Fahimeh Ramezani Tehrani, Factors affecting sexual function in menopause: A review article, Taiwanese Journal of Obstetrics and Gynecology, Volume 55, Issue 4, 2016, Pages 480-487, ISSN 1028-4559, https://doi.org/10.1016/j.tjog.2016.06.001.
    5. Raphael C. Parente, Eduardo Faerstein, Roger Keller Celeste, Guilherme L. Werneck,
    6. Raphael C. Parente, Eduardo Faerstein, Roger Keller Celeste, Guilherme L. Werneck, The relationship between smoking and age at the menopause: A systematic review, Maturitas, Volume 61, Issue 4, 2008, Pages 287-298, ISSN 0378-5122, https://doi.org/10.1016/j.maturitas.2008.09.021.

  • Erection and smoking

    Erection and smoking

    Few men make the connection between smoking and their sexual performance. Yet there is a well-established link between smoking and difficulty achieving and maintaining an erection (erectile dysfunction, ED). This is what motivates many smokers to quit smoking. Here is what scientific studies show, and what improves when you quit smoking.

    How smoking damages erections

    An erection is a vascular event. Sexual arousal triggers nerve signals that prompt the cells lining the penile arteries to release nitric oxide, a gas that relaxes smooth muscle and lets blood flood the erectile tissue. Anything that interferes with nitric oxide, or with the arteries themselves, interferes with erections.

    Tobacco smoke does both. It contains thousands of chemicals, many of which generate oxidative stress, a kind of cellular wear that damages the endothelium, the thin layer lining blood vessels. Damaged endothelium produces less nitric oxide and breaks it down faster. Over years, smoking also drives atherosclerosis, the buildup of fatty plaque that narrows arteries.

    Size matters here. The penile arteries are only a millimeter or two across, much narrower than the coronary arteries. A given amount of vascular damage can therefore show up as erectile trouble before it causes chest pain or any other symptom. Urologists and cardiologists have long noted that ED can precede heart disease by a few years, and some describe it as an early warning sign.

    Other components of smoke add to the problem. Carbon monoxide binds to hemoglobin more readily than oxygen does, reducing the oxygen the blood can deliver. Nicotine stimulates the sympathetic nervous system, which tightens blood vessels and promotes contraction of the smooth muscle that has to relax for an erection to occur. Animal studies have also found structural changes in erectile tissue after prolonged exposure to smoke, including loss of smooth muscle and increased fibrous tissue. Whether smoking meaningfully lowers testosterone in men is less settled, and the evidence there is inconsistent.

    How much higher is the risk?

    A systematic review and meta-analysis pooled data from observational studies and found that current smokers had roughly 1.5 times the risk of ED compared with men who had never smoked. Risk generally climbs with the number of cigarettes per day and the number of years smoked, a dose-response pattern that strengthens the case for a causal link rather than a coincidence.

    The effect is not confined to older men. ED is often assumed to be a problem of the 60s and 70s, but studies of younger men have found smoking to be one of the more consistent modifiable risk factors among those who develop ED in their 30s and 40s. Smoking also compounds other risks.

    What happens when you quit

    The same meta-analysis revealed that the risk among former smokers fell halfway between that of people who had never smoked and that of current smokers. Another synthesis found that population studies suggest that former smokers may not fully return to the same level of ED risk as non-smokers. However, smaller studies indicate that younger men (under 50) may have a better chance of improving erectile function after stopping smoking. Quitting early appears to offer the greatest chance of improvement. In men with severe cardiovascular disease and erectile dysfunction, however, the damage may be too advanced for quitting smoking alone to make a significant difference.

    This is consistent with what we know about vascular recovery. Endothelial function begins to improve a few weeks after the last cigarette, and carbon monoxide clears from the blood within one or two days, but some damage may be permanent. Damage that has accumulated over several decades may not fully reverse, which is one argument for quitting sooner rather than later.

    Quitting can also make ED treatment work better. Drugs such as sildenafil and tadalafil depend on the nitric oxide pathway, and men with healthier blood vessels generally respond to them better.

    A practical point

    Men with persistent erectile problems should see a doctor whether or not they smoke, because there are effective and safe treatments for ED. In addition, ED can precede or signal existing cardiovascular disease, and a medical visit is worthwhile.

    For smokers, a medical visit is also a good moment to ask about smoking cessation support. Nicotine replacement, prescription medications such as varenicline or cytisine, and counseling roughly double the odds of quitting successfully compared with going it alone.

    For many men, the prospect of regaining sexual function is a more immediate motivation than the abstract threat of cancer decades away. The research suggests it is also a realistic one.


    Please use the Comments field below to share your experience or to suggest improvements to this article.


    Rate this article by clicking on the desired number of stars:
    (No Ratings Yet)


    References:

    Cao S, Yin X, Wang Y, Zhou H, Song F, Lu Z. Smoking and risk of erectile dysfunction: systematic review of observational studies with meta-analysis. PLoS One. 2013;8(4):e60443. https://doi.org/10.1371/journal.pone.0060443

    Mark S Allen, Rita C Tostes, Cigarette smoking and erectile dysfunction: an updated review with a focus on pathophysiology, e-cigarettes, and smoking cessation, Sexual Medicine Reviews, Volume 11, Issue 1, January 2023, Pages 61–73, https://doi.org/10.1093/sxmrev/qeac007

    Kovac, J.R., Labbate, C., Ramasamy, R., Tang, D. and Lipshultz, L.I. (2015), Effects of cigarette smoking on erectile dysfunction. Andrologia, 47: 1087-1092. https://doi.org/10.1111/and.12393

  • Nicotine

    Nicotine

    In this section, you will find several articles explaining everything you need to know about nicotine: a test to help you determine how much nicotine you need, the amount of nicotine in a cigarette, the optimal nicotine concentration for your e-liquids, and the effects of nicotine on health, nicotine salts.

  • Nicotine: health effects

    Nicotine: health effects

    Here is what experts consider to be the current evidence regarding the health effects of nicotine. The main message is that nicotine is addictive, but poses few direct health risks when separated from tobacco smoke. People who do not already smoke should not use nicotine.

    • Addiction is the Main Risk: Nicotine is the chemical in tobacco that causes addiction (dependence) by triggering pleasure and making people want to avoid withdrawal symptoms (cravings).
    • Tobacco Smoke is the Danger: The thousands of toxic and cancer-causing chemicals in tobacco smoke—not the nicotine—are what make smoking lethal.
    • Aids to Quitting Smoking: Nicotine-containing products like Nicotine Replacement Therapy (NRT: patches, gum) and vapes (e-cigarettes) are effective tools to help people quit smoking by managing cravings without the severe harm of tobacco.
      • Vaping is recommended as a quit aid and is considered significantly less harmful than smoking.
      • Evidence shows people using nicotine vapes are almost twice as likely to quit successfully compared to those using NRT.
    • Who Should Use Nicotine: Nicotine products are primarily for people who already smoke and are trying to quit. They should not be used by non-smokers.

    Specific Health Impacts of Nicotine (Separate from Smoking)

    The evidence suggests that many of the severe health problems linked to smoking are not caused by nicotine alone:

    • Heart Health: Nicotine can cause a temporary, short-term rise in heart rate and blood pressure. However, long-term evidence of harm is lacking. Smokers who completely switch to vapes or NRT often see significant and early improvements in their vascular health.
    • Cancer: The research consensus is that nicotine does not cause cancer.
    • Brain Development: There is limited evidence that nicotine significantly impacts cognitive function in humans, and separating its effects from smoking is difficult. Pre-existing factors may also play a role.
    • Mental Health: While smoking is linked to conditions like depression, nicotine itself does not appear to be the main driver; other chemicals in tobacco smoke play a larger role.
    • Toxicity: At very high levels, nicotine can cause acute side effects like nausea and dizziness, but users quickly learn to avoid these toxic doses.

    Reference: ASH. Evidence summary: The health effects of nicotine. November 2025. ASH-evidence-brief-on-nicotine-V6-Nov25.pdf


  • 10 policies against smoking

    10 policies against smoking

    Smoking remains a scourge on public health and a major factor of healthcare costs, but the good news is that governments worldwide have effective and proven tools at their disposal to combat it. This article presents the ten most effective policy measures, backed by scientific evidence, that can significantly reduce smoking and save lives.

    These policies work by either making smoking less appealing and accessible, or by empowering smokers to quit.


    Economic Approach

    1. Raise Taxes on Tobacco Products

    This is widely considered the single most effective policy for reducing tobacco consumption. Significant and regular increases in excise taxes make tobacco products less affordable, discouraging young people from starting and incentivizing current users to quit. For every 10% price increase, studies show a significant reduction in overall consumption, with the greatest impact seen among youth and low-income populations.

    2. Eliminate Tax-Free and Duty-Free Sales

    By removing tax exemptions for tobacco sold at airports and border crossings, governments close a loophole that allows products to be sold at artificially low prices. This policy maintains the price disincentive and prevents cheap tobacco from undermining local taxation efforts.

    Smoke-free laws and clean air

    3. Implement Comprehensive Smoke-Free Laws

    Laws mandating 100% smoke-free indoor public places, workplaces, restaurants, and bars protect non-smokers from the harms of secondhand smoke. Furthermore, these policies change social norms, making smoking less visible, less socially acceptable, and providing a powerful incentive for smokers to quit. Well-enforced bans have been shown to reduce smoking prevalence itself.

    Extending smoke-free regulations to include outdoor areas—such as parks, beaches, school grounds, and hospital entrances—further de-normalizes smoking, protects children from exposure, and reinforces the public health message that smoking is not a typical behaviour.

    Replace combustible products with smokefree products

    4. Accelerate the replacement of cigarettes with non-combustible products

    The tobacco market is undergoing rapid change, with cigarettes becoming an obsolete and inferior product, replaced by non-combustible alternatives.

    It is essential to accelerate the transition of smokers to these new products, while implementing effective and proportionate policies to prevent young non-smokers from starting to use nicotine or tobacco.

    5. Providing truthful information and combating disinformation

    Misinformation about harm reduction and non-combustible nicotine and tobacco products is ubiquitous. Governments should support the creation and dissemination of truthful, balanced, and honest information on these topics.

    Health warnings and bans on advertising

    6. Enforce Comprehensive Bans on Tobacco Advertising, Promotion, and Sponsorship

    Tobacco advertising recruits new users and undermines quit attempts. A total ban on all forms of advertising—including in traditional media, online, at the point of sale, and through product placement or sponsorship—is highly effective at reducing tobacco initiation, particularly among youth.

    7. Mandate Graphic Health Warnings and Plain Packaging

    Removing all branding, colours, and promotional elements from tobacco packaging (plain packaging) and requiring large, graphic health warnings that cover at least 50% (and ideally much more) of the pack surface reduces the product’s appeal and increases consumer awareness of the harms. This policy eliminates the pack as a marketing tool.

    Helping smokers quit

    8. Provide Accessible and Affordable Smoking Cessation Services

    While policies reduce demand, many addicted smokers need help to quit. Governments must invest in comprehensive cessation support, including:

    • Toll-free national quitlines.
    • Coverage for proven therapies (like NRT and prescription medicines such as varenicline and cytisine) and behavioral counselling through national health insurance programs.
    • Integrating ‘Ask, Advise, Refer’ protocols into routine healthcare.

    9. Run Sustained, High-Impact Mass Media Campaigns

    Hard-hitting, professionally produced anti-tobacco media campaigns that clearly communicate the health risks and benefits of quitting are highly effective. These campaigns should be sustained over time and run at high frequency to ensure maximum reach and impact, reinforcing the message that help is available.

    Monitor tobacco use and evaluate interventions

    10. Monitor tobacco use and evaluate campaigns and policies

    It is crucial to monitor tobacco and nicotine use in each population subgroup, and to assess the intended and unintended effect of all interventions, campaigns, policies, treatments and other anti-tobacco measures.


    Use the ‘Comments’ field below to share your experience or to suggest improvements to this article.


  • How much nicotine is in a cigarette?

    How much nicotine is in a cigarette?

    Nicotine is what keeps you smoking, and it is interesting to know how much nicotine is in a cigarette, how much you inhale, and why cigarettes deliver it so effectively. Understanding this makes it easier to choose the right support when you quit smoking, the right nicotine concentration for your e-liquids, and the right dosage for your nicotine medications

    By Jean-François Etter, professor of public health.


    How much nicotine is in a cigarette and how much do you inhale?

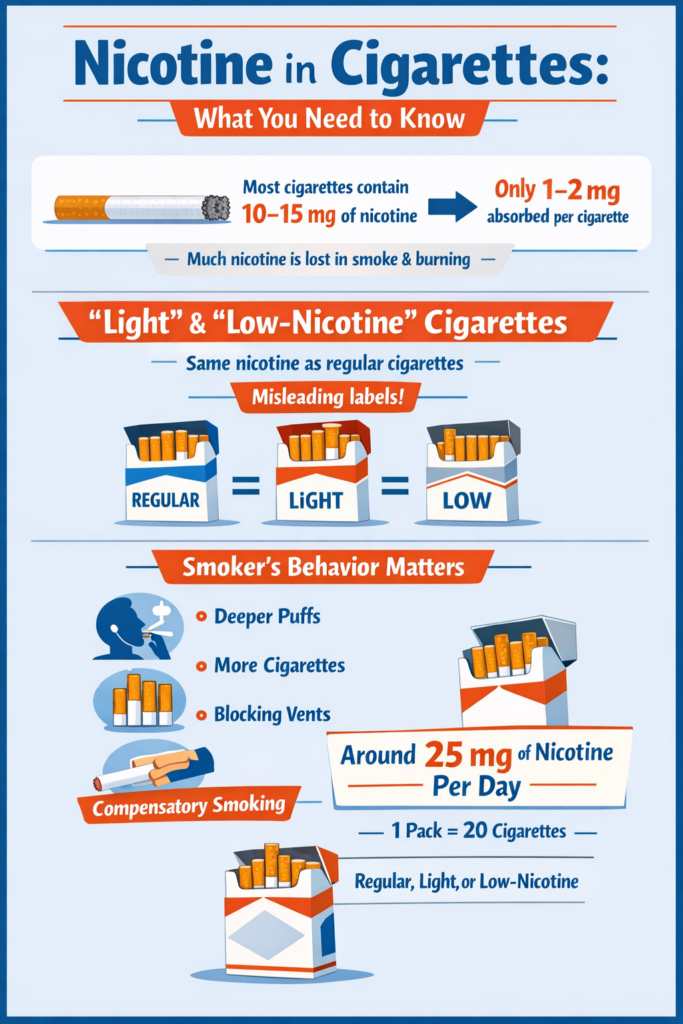
    Most commercial cigarettes contain 10 to 15 mg of nicotine in the tobacco. You don’t absorb all of that. Much of it is destroyed by burning, left in the butt, or lost in the smoke that drifts away between puffs. A smoker absorbs 1 to 2 mg per cigarette. That is enough to create and maintain nicotine addiction.

    Why cigarettes are so addictive

    Speed of delivery is the key factor. When you smoke a cigarette, the inhaled nicotine reaches the brain within about 10 seconds, triggering a release of dopamine that feels rewarding or calming. Nicotine level peaks in the blood after 5 to 8 minutes, then nicotine clears from the body fairly quickly, and levels fall by half within about 90 minutes, and withdrawal symptoms such as irritability, cravings and poor concentration begin to build. The next cigarette relieves them, and the cycle repeats. Over time the brain adapts and comes to expect regular doses.

    Manufacturers have also designed cigarettes to make nicotine delivery fast, stable and reliable, through tobacco blending, chemical additives that make the smoke easier to inhale, and by spraying nicotine on tobacco during manufacture. The amount of nicotine in a commercial cigarette is measured with the same precision as the active ingredients in medications. In fact, a cigarette is a highly sophisticated nicotine delivery device, manufactured almost like a medication.

    “Light”, “mild” and “low-nicotine” cigarettes

    Cigarettes once sold as “light”, “mild” or “low nicotine” (labels now banned in many countries) contain about as much nicotine in the tobacco as regular ones. They produce lower nicotine yields on testing machines because tiny ventilation holes near the filter dilute the smoke, but smokers don’t smoke like machines. Because the brain wants its usual dose, people who smoke these cigarettes tend to compensate by:

    • taking deeper or longer puffs,
    • smoking more cigarettes, and
    • covering the vent holes with their fingers or lips.

    The result is that they get a roughly similar dose of nicotine and the same toxic smoke for regular and “light” cigarettes.

    Genuinely very-low-nicotine cigarettes (VLNC), which contain almost no nicotine in the tobacco, are different. In research trials they have reduced dependence and the number of cigarettes smoked, which is why some governments are considering limits on nicotine content, but this policy is controversial, because some experts think that people will not use VLNC in the long term. VLNC are not widely available, and they are not a safe cigarette either, since the smoke is still harmful.

    Nicotine is addictive, but smoke is what does most of the damage

    Nicotine is most addictive when it is inhaled, and the manufactured cigarette is by far the most addictive of all nicotine-delivery products. Nobody is addicted to the nicotine patch, because it delivers nicotine too slowly. However, even with non-inhaled products, nicotine temporarily raises heart rate, and it should be avoided in pregnancy unless a doctor advises otherwise. But the cancers, lung diseases and heart diseases caused by smoking comes from burning tobacco and inhaling smoke: tar, carbon monoxide and thousands of other chemicals. This is why delivering nicotine without smoke is much safer than smoking, and why it can help you stop smoking.

    What can help you quit smoking?

    If you are addicted to nicotine, it is important to continue using nicotine after you quit smoking in order to avoid withdrawal symptoms and prevent a relapse.

    Nicotine replacement therapy (NRT) in the form of patches, gum, lozenges, tablets, inhalers or sprays is safe and gives you nicotine at a slower, steadier rate than a cigarette, without the smoke. This relieves cravings and withdrawal while you break the habit. Because nicotine is absorbed gradually rather than hitting the brain within seconds, NRT has a much lower potential for dependence than cigarettes, though a small number of people do continue using nicotine gums for longer than planned. Nobody is addicted to the nicotine patch, because of its very slow nicotine delivery.

    • Combination NRT works better. Using a patch for steady background nicotine plus a fast-acting form (gum, lozenge or spray) for sudden cravings improves the chances of quitting compared with a single product.
    • Dose matters. Heavier smokers (for example those who smoke 10 or more cigarettes a day, or light up within 30 minutes of waking) usually need a higher-strength patch or gum. Too little nicotine is a common reason for relapse. A pharmacist or doctor can help you choose the best product and the right dosage.
    • Prescription medicines such as varenicline and cytisine / cytisinicline reduce cravings and the reward from smoking, and in studies they are among the most effective options. Bupropion is another choice. Availability varies by country.
    • Nicotine e-cigarettes have helped many people stop smoking, and recent reviews suggest they are more effective than NRT and as affective as varenicline. They are much less harmful than cigarettes, but not risk-free, and long-term effects are still being studied. They are intended for smokers who want to quit, not for non-smokers. Read our article on the best nicotine concentration in e-liquids, based on your personal needs.
    • Nicotine pouches have been studied less, and rules on their sale differ between countries.
    • Support increases success. Counselling, quitline calls and peer groups help with the habits, routines and emotions linked to smoking, and work well alongside medication.

    Find out how much nicotine you need

    Take our quiz to estimate how much nicotine you inhale (or inhaled) as a smoker, and what dosage of nicotine suits you best.

    What to expect after quitting

    Withdrawal symptoms usually peak within the first weeks and then ease. These include cravings, irritability, trouble sleeping, difficulty concentrating and increased appetite and weight gain. These symptoms are attenuated by nicotine medications. Cravings come in waves that pass, even if you do nothing. Slips happen and are not failure. Many people need more than one attempt, and each attempt teaches you something.

    Talk to a professional if you…

    • are pregnant or breastfeeding,
    • have heart disease, or
    • take regular medication or have a medical condition.

    Most people can safely use NRT, and the risks of continuing to smoke are far greater, but a doctor or pharmacist can tailor advice to you.


    Rate this article by clicking on the desired number of stars:
    (3 votes, average: 5.00 out of 5)


    Please use the “Comments” field below to share your experience or suggest improvements to this article.


    References:

    Theodoulou A, Chepkin SC, Ye W, Fanshawe TR, Bullen C, Hartmann-Boyce J, Livingstone-Banks J, Hajizadeh A, Lindson N. Different doses, durations and modes of delivery of nicotine replacement therapy for smoking cessation. Cochrane Database of Systematic Reviews 2023, Issue 6. Art. No.: CD013308. https://doi.org/10.1002/14651858.CD013308.pub2

    Djordjevic, M.V., Doran, K. . (2009). Nicotine Content and Delivery Across Tobacco Products. In: Henningfield, J.E., London, E.D., Pogun, S. (eds) Nicotine Psychopharmacology. Handbook of Experimental Pharmacology, vol 192. Springer, Berlin, Heidelberg. https://doi.org/10.1007/978-3-540-69248-5_3

    Djordjevic, M.V., Doran, K. . (2009). Nicotine Content and Delivery Across Tobacco Products. In: Henningfield, J.E., London, E.D., Pogun, S. (eds) Nicotine Psychopharmacology. Handbook of Experimental Pharmacology, vol 192. Springer, Berlin, Heidelberg. https://doi.org/10.1007/978-3-540-69248-5_3

    Martin J. Jarvis, Richard Boreham, Paola Primatesta, Colin Feyerabend, Andrew Bryant, Nicotine Yield From Machine-Smoked Cigarettes and Nicotine Intakes in Smokers: Evidence From a Representative Population Survey, JNCI: Journal of the National Cancer Institute, Volume 93, Issue 2, 17 January 2001, Pages 134–138, https://doi.org/10.1093/jnci/93.2.134

    Malson JL, Sims K, Murty R, et al. Comparison of the nicotine content of tobacco used in bidis and conventional cigarettes. Tobacco Control 2001;10:181-183. https://doi.org/10.1136/tc.10.2.181


  • Nicotine patch

    Nicotine patch


    An effective tool for quitting smoking

    The nicotine patch is a small, bandage-like patch that you apply directly to your skin, typically on your arm or torso. It’s designed to deliver a controlled, steady dose of nicotine into your bloodstream throughout the day. It provides you with nicotine in a controlled manner, without the harmful substances (tar, carbon monoxide) found in cigarette smoke.

    It is designed to alleviate the discomfort associated with cigarette withdrawal symptoms (craving for cigarettes, irritability, bad mood, depression, anxiety, difficulty consentrating, trouble sleeping, increased appetite and weight gain).

    How Does the Patch Work?

    The nicotine patch slowly releases nicotine through your skin, which is then absorbed by your body.

    The patch can be used by smokers who wish to quit smoking, but also by those who are not yet ready to quit and who continue to smoke while wearing the patch:

    • After you quit smoking, the patch relieves cravings and other nicotine withdrawal symptoms, so that you suffer less during the first days, weeks and months after quitting.
    • The patch increase your chances of successfully quitting smoking.
    • Smokers who are not ready to quit immediately can use nicotine patches for a few weeks before quitting smoking, in addition to cigarettes. This way, most of their nicotine needs will be met by the patch, they will smoke fewer cigarettes, and it will be easier for them to quit after a few weeks of combined use.
    • Smokers who do not wish to quit smoking, or feel unable to do so, can use nicotine patches to reduce their cigarette consumption. This means that part of their nicotine requirement will be satisfied by the patch, and they will smoke fewer cigarettes, thereby inhaling less smoke and fewer toxic components present in cigarette smoke. This dual use can be continued in the long term, over several months or years.

    Is the patch effective to quit smoking?

    In smokers willing to quit, a synthesis of 51 high-quality studies involving 25,754 participants concluded that nicotine patches increase their chances of quitting smoking by a factor of 1.64 (i.e. +64%), compared to a control group that did not use patches. However, it is difficult to quit smoking, and the median quit rate in the control group was only xx per cent after 6 months, while the quit rate in the group using the patch was xx per cent. This shows that the patch is effective, but that it only increases your chances of quitting smoking by a few percentage points.

    To increase your chances of quitting smoking, you can combine two nicotine medications, e.g. patch and gum, or patch and inhaler, or patch and tablet. This will further increase your chances of quitting by a factor x1.27 (i.e. +27%).

    There is evidence that higher-doses patches (21-25 mg) are more effective than lower doses patches (14-15 mg), and that patches with 42-44 mg are as effective as patched with 21-22 mg.

    The Importance of compliance and of not smoking after you quit, not even a puff

    For the treatment to be effective, you must follow the instructions. It is essential that you use the patch every day, at the recommended dosage, for 3 months after quitting smoking, without stopping the treatment prematurely. If you do not do so, you increase the risk of relapse.

    You can smoke while wearing the patch; it is not dangerous. However, it is best not to smoke at all after quitting, even a single puff, as this increases the risk of relapse.

    Consulting a healthcare professional (doctor, psychologist, pharmacist) can significantly increase your chances of success.

    How to Use the Patch?

    Some brands of patches are designed to be worn for 16 hours a day, from morning until bedtime. The idea is to simulate the fluctuations in nicotine levels experienced by a smoker without supplying nicotine during sleep, which could disrupt sleep. Other brands are designed to be worn for 24 hours. The idea is to reduce the urge to smoke and withdrawal symptoms in the morning.

    With the 16-hour patch that you remove before going to bed, you may wake up with very low nicotine levels in your blood and experience cigarette cravings and other nicotine withdrawal symptoms in the morning. The patch slowly releases nicotine through the skin, and you will not feel its full effects until two hours after applying it. Therefore, you should use the patch in combination with a faster-acting product, such as nicotine gum or lozenges, to avoid withdrawal symptoms in the morning.

    Dosage depends on your initial cigarette consumption:

    Heavy smokers (more than 15 cigarettes/day): Start with the highest dose (25 mg/16h) for 8 weeks, then reduce (15 mg/16h for 2 weeks, then 10 mg/16h for 2 weeks).

    Moderate/light smokers (fewer than 15 cigarettes/day): Start directly with the medium dose (15 mg/16h) for 8 weeks, then switch to the low dose (10 mg/16h) for 4 weeks.

    Treatment lasts 3 months. It is very important not to stop treatment prematurely, as this would increase the risk of relapse.

    Practical Tip: Change the application site every day to minimize skin irritation.

    Precautions and Contraindications

    The nicotine patch should not be used by non-smokers or non-users of tobacco or e-cigarettes, children under 12, and in principle, adolescents, unless there are already addicted to cigarettes or e-cigarettes.

    Health Conditions:

    If you suffer from recent or severe heart problems (recent heart attack, unstable or worsening angina, uncontrolled high blood pressure), or other conditions such as diabetes, kidney/liver diseases, or epilepsy, you must consult your doctor before starting treatment.

    Pregnancy and Breastfeeding:

    Nicotine, even in the form of a medication, can harm the fetus or infant. Pregnant or breastfeeding women should only use the nicotine patch after consulting a healthcare professional. If smoking cessation is not achieved, flexible-dose nicotine products (like gum or lozenges) are preferred.

    What Side Effects Can You Expect?

    Side effects of the patch are often confused with cigarette withdrawal symptoms.

    Common side effects of the patch: Itching at the application site, headache, nausea, or vomiting. Not to be confused with cigarette withdrawal symptoms: Irritability, depression, anxiety, bad mood, difficulty concentrating, sleep disturbances, increased appetite, or smoking cravings.

    Most skin reactions are mild and disappear quickly after removing the patch. If you experience severe effects (chest pain, irregular pulse), stop treatment and seek medical advice.

    If you absorb too much nicotine, you may feel nauseous, dizzy or weak, and have a bad taste in your mouth, similar to the feeling you get when you smoke too much. If this happens, remove the patch immediately and the effect will disappear after a few minutes. There is no risk of nicotine overdose with nicotine patches in former smokers or tobacco users.

    The nicotine patch is a valuable tool, but ultimate success depends on your willingness to quit smoking, your ability to avoid places where you used to smoke and the presence of other smokers, and, ideally, medical supervision.


    Rate this article by clicking on the desired number of stars:
    (1 votes, average: 5.00 out of 5)

    Please use the “Comments” field below to share your experience or suggest improvements to this article.