Help to stop smoking

Category: Diseases

  • Wrinkles, skin health

    Wrinkles, skin health

    You can’t hide what smoking does to your skin. It’s your body’s biggest organ, and it takes a hit with every cigarette. Wrinkles are only part of the story: smoking also changes how your skin heals, how it fights off germs, and how it handles the sun.

    More wrinkles

    Studies keep finding the same thing. Smokers get wrinkles earlier and worse than non-smokers, even when the amount of sun they’ve had is the same. And it adds up, the more you smoke each day, and the longer you’ve been at it, the more the skin ages.

    How smoking ages your skin from the inside

    Your skin stays firm and bouncy thanks to two proteins. Collagen gives it strength and structure. Elastin lets it spring back after you stretch or squeeze it. Smoking attacks both in four main ways:

    • Smoking floods your body with damaging chemicals. Cigarette smoke has thousands of compounds, and many of them create free radicals. These are unstable molecules that damage healthy cells. Your skin normally fights back with antioxidants like vitamins C and E, but smokers use these up fast. With fewer defences, collagen breaks down and your body struggles to make more.
    • Smoking switches on enzymes that eat collagen. In smokers, collagen gets destroyed faster than it’s rebuilt, and the deeper layer of skin slowly gets thinner and weaker.
    • Smoking cuts off the blood supply. Nicotine narrows your blood vessels, and the tiny ones that feed your skin suffer most. Less blood means less oxygen and fewer nutrients, so your skin can’t repair itself properly. This is why some smokers have a dull, greyish tone.
    • Smoking lowers oestrogen in women. Oestrogen helps keep skin thick, moist and full of collagen. Smokers tend to have lower levels, which is one reason female smokers often show more skin ageing than male smokers.

    Smoking plus sun is a bad mix

    Ultraviolet (UV) light from the sun is the biggest outside cause of early skin ageing. It damages the DNA in skin cells, breaks down collagen and elastin, and causes uneven colouring.

    Smoking and sun damage don’t just stack on top of each other. They make each other worse. Both trigger collagen-eating enzymes, and both create free radicals. If you smoke and also spend a lot of time in the sun without protection, your skin is under attack from two sides at once.

    There’s a cancer link too. Smoking isn’t as closely tied to melanoma as sun exposure is, but it does seem to raise the risk of some other skin cancers, especially squamous cell carcinoma. Smoking also weakens the immune system, so your skin may be slower to spot and destroy abnormal cells before they spread.

    Why cuts and wounds heal slowly

    Smokers are much more likely to have problems after surgery. Wounds can split open, get infected, or heal into worse scars. In some cases, smoking is a big enough risk that a surgeon may advise waiting on an optional operation until after the patient quits smoking.

    Here’s why. Nicotine narrows blood vessels, so less oxygen and fewer nutrients reach the wound. Your body needs both to build new collagen. Carbon monoxide from smoke makes it worse. It gets into your blood and takes the place of oxygen on your red blood cells, so they carry less of it around.

    It isn’t only surgery. Everyday cuts and scrapes take longer to heal in smokers. Long-lasting wounds like leg ulcers are more common and harder to treat. Even spots and other skin problems can hang around longer.

    Smoking and skin infections

    Your skin is your first line of defence against germs. It works as a physical barrier, and it has immune cells watching for trouble. Smoking weakens this at several levels.

    Langerhans cells sit in the top layer of your skin and spot invaders. Smokers have fewer of them, and they don’t work as well. That means infections are more likely to get going before your body notices. Smokers get more skin infections, including fungal ones like candidiasis, and they’re more likely to get a bacterial infection after an injury. Poor blood flow, a weaker immune response and slow healing all help germs settle in and stay.

    The good news: your skin can bounce back

    Skin has a real ability to recover once you quit smoking. Blood flow to your skin starts improving within weeks. As your body goes back to making collagen normally, skin quality gets better over time. The biggest changes usually show up in younger people who haven’t smoked for long. Still, plenty of long-term smokers say their skin tone and texture look better within months or years of stopping.

    Some damage, especially deep changes to collagen and elastin, can’t be fully undone. But quitting stops the damage from getting worse and gives your skin its best chance to repair itself. Add sun protection, plenty of water and a diet full of fruit and vegetables, and the difference can be big.

    Every cigarette you don’t smoke is a small win for your skin, and for a face that looks your real age.


    Use the Comments field below to share your experience or to suggest improvements to this article.


    References:

    Akimichi Morita, Tobacco smoke causes premature skin aging,
    Journal of Dermatological Science, Volume 48, Issue 3, 2007,
    Pages 169-175, ISSN 0923-1811, https://doi.org/10.1016/j.jdermsci.2007.06.015.

    Ortiz, A. and Grando, S.A. (2012), Smoking and the skin. International Journal of Dermatology, 51: 250-262. https://doi.org/10.1111/ .1365-4632.2011.05205.x

    Sørensen, L. (2012). Wound Healing and Infection in Surgery: The Pathophysiological Impact of Smoking, Smoking Cessation, and Nicotine Replacement Therapy A Systematic Review. Annals of Surgery, 255(6), 1069–1079. https://doi.org/10.1097/SLA.0b013e31824f632d



  • Asthma

    Asthma

    Asthma is a chronic condition in which the airways become inflamed, narrowed, and overly sensitive. Smoking has a profound impact on asthma, not only increasing the risk of developing the disease but also making symptoms more severe and harder to control.


    How smoking causes and worsens asthma

    Cigarette smoke contains thousands of chemicals that irritate and damage the airways. In people with asthma, the airways are already inflamed and reactive. Smoking adds a constant source of irritation, which intensifies this inflammation and makes the airways even more sensitive to triggers such as allergens, cold air, or exercise.

    Over time, smoking alters the structure of the airways. It increases mucus production, damages the lining of the lungs, and reduces the effectiveness of the natural defense mechanisms that clear irritants. This leads to more frequent symptoms such as wheezing, coughing, chest tightness, and shortness of breath.

    Smoking also reduces the effectiveness of asthma medications, particularly inhaled corticosteroids, which are the cornerstone of asthma treatment. As a result, smokers with asthma often experience poorer disease control, more frequent exacerbations, and a higher risk of hospitalization.

    In some individuals, long-term smoking can lead to a combination of asthma and chronic obstructive pulmonary disease (often referred to as asthma-COPD overlap), which is associated with more severe and persistent airflow limitation.


    The impact of secondhand smoke on asthma

    Even if you do not smoke, exposure to secondhand smoke can significantly affect asthma. In children, it is a major risk factor for developing asthma in the first place. In both children and adults who already have asthma, secondhand smoke can trigger attacks and worsen daily symptoms.

    Regular exposure to smoke increases airway inflammation and sensitivity. It can lead to more frequent use of rescue inhalers, more missed school or work days, and a reduced quality of life. For people with severe asthma, even brief exposure can provoke serious symptoms.

    Creating a smoke-free environment at home and in cars is therefore critical, especially when someone in the household has asthma.


    How quitting smoking improves asthma

    Quitting smoking is one of the most effective ways to improve asthma control. Once exposure to smoke stops, airway irritation begins to decrease, and the lungs start to recover.

    People who quit smoking often notice that their symptoms become less frequent and less severe. They may experience fewer asthma attacks, better breathing, and improved response to medications. Over time, lung function can stabilize or even improve, particularly if quitting occurs before significant long-term damage has developed.

    Quitting also reduces the risk of developing more severe lung disease and helps protect against infections that can trigger asthma exacerbations.


    How quickly do improvements occur?

    The timeline of improvement after quitting smoking varies depending on the severity and duration of asthma, as well as how long the person has smoked.

    Within the first few days to weeks, carbon monoxide levels drop and oxygen delivery improves. Some people begin to notice easier breathing and less coughing within the first two to four weeks, as airway irritation starts to subside.

    Over the next one to three months, lung function can improve measurably. Airways become less reactive, and the frequency of symptoms and exacerbations often decreases. Medications may start to work more effectively during this period.

    In people with mild to moderate asthma, significant improvements are often seen within a few months, with better overall control and fewer limitations in daily activities.

    For those with more advanced or long-standing asthma, especially if there has been structural damage to the airways, improvements may be slower and less complete. However, even in these cases, quitting smoking reduces further decline, decreases exacerbations, and improves quality of life.

    After one year and beyond, the benefits continue to accumulate. The risk of severe complications decreases, and lung function decline slows compared to those who continue smoking.


  • Angina pectoris

    Angina pectoris

    Angina pectoris is chest pain caused by reduced blood flow to the heart, most often due to narrowed coronary arteries. Smoking is a major cause and greatly worsens prognosis. With proper treatment and, above all, quitting smoking, symptoms can be controlled and the risk of heart attack and early death can be significantly reduced.

    Angina pectoris is often described as a warning signal from the heart. It is not a heart attack, but it is closely linked to the same disease process and should never be ignored. The term refers to chest pain or discomfort caused by reduced blood flow to the heart muscle, most commonly as a result of narrowed coronary arteries.

    Angina is widespread, particularly in countries with aging populations. Millions of people worldwide live with this condition, and it is more common after the age of 50. Men are affected earlier in life, while women tend to develop symptoms later, often after menopause. Despite advances in prevention and treatment, angina remains a major contributor to disability and healthcare use because it signals underlying coronary artery disease, one of the leading causes of death globally.

    The root cause of angina is usually atherosclerosis, a gradual buildup of fatty deposits inside the arteries that supply the heart. Smoking plays a central role in this process. Chemicals in tobacco smoke damage the lining of blood vessels, promote inflammation, and accelerate plaque formation, while also increasing the tendency of blood to clot. High blood pressure, elevated cholesterol, diabetes, physical inactivity, and chronic stress further increase the strain on the heart. When the heart muscle needs more oxygen, such as during physical exertion or emotional stress, narrowed arteries may not be able to deliver enough blood, triggering pain.

    Prevention begins with addressing these risk factors, and quitting smoking stands out as the single most powerful step. Stopping smoking improves blood vessel function and reduces the risk of progression to heart attack. Regular physical activity, a balanced diet low in saturated fats and salt, weight control, and effective management of blood pressure and diabetes all contribute to protecting the heart. For people with angina, these measures are not optional lifestyle advice but an essential part of treatment.

    The symptoms of angina are often described as pressure, tightness, or a squeezing sensation in the chest, sometimes spreading to the arms, neck, jaw, or back. Shortness of breath, nausea, sweating, or unusual fatigue may accompany the pain. In many cases, symptoms appear predictably with effort and ease with rest. However, angina can sometimes be less typical, particularly in women and people with diabetes, which can delay recognition and diagnosis.

    Doctors diagnose angina by combining a careful clinical history with tests that assess how the heart functions under stress. An electrocardiogram may show changes during pain or exercise, while imaging tests can reveal areas of the heart that receive too little blood. In some cases, coronary angiography is needed to directly visualize narrowed arteries and guide treatment decisions.

    The outlook for people with angina varies. Stable angina, when symptoms are predictable and well controlled, can often be managed for many years. However, angina also signals a higher risk of heart attack, heart failure, and sudden cardiac death, especially if risk factors such as smoking persist. Without proper treatment and lifestyle changes, the disease tends to progress as arterial narrowing worsens over time.

    Treatment aims to relieve symptoms, improve quality of life, and reduce the risk of serious complications. Medications can lower the heart’s oxygen demand, improve blood flow, and prevent clot formation. In more severe cases, procedures to open or bypass blocked arteries may be necessary. Yet even the most advanced treatments cannot fully counteract the harm caused by continued smoking. Patients who quit smoking after an angina diagnosis significantly reduce their risk of heart attack and death.

    Survival rates for people with angina have improved markedly with modern care, but they depend heavily on individual choices. Those who stop smoking, adhere to treatment, and manage other risk factors can expect a near-normal life expectancy in many cases. By contrast, continued tobacco use sharply worsens outcomes, making angina not just a medical condition but a powerful reminder that quitting smoking is a decisive step toward protecting the heart and prolonging life.


    Use the ‘Comments’ field below to share your experience or to suggest improvements to this article.


  • Laryngeal cancer

    Laryngeal cancer

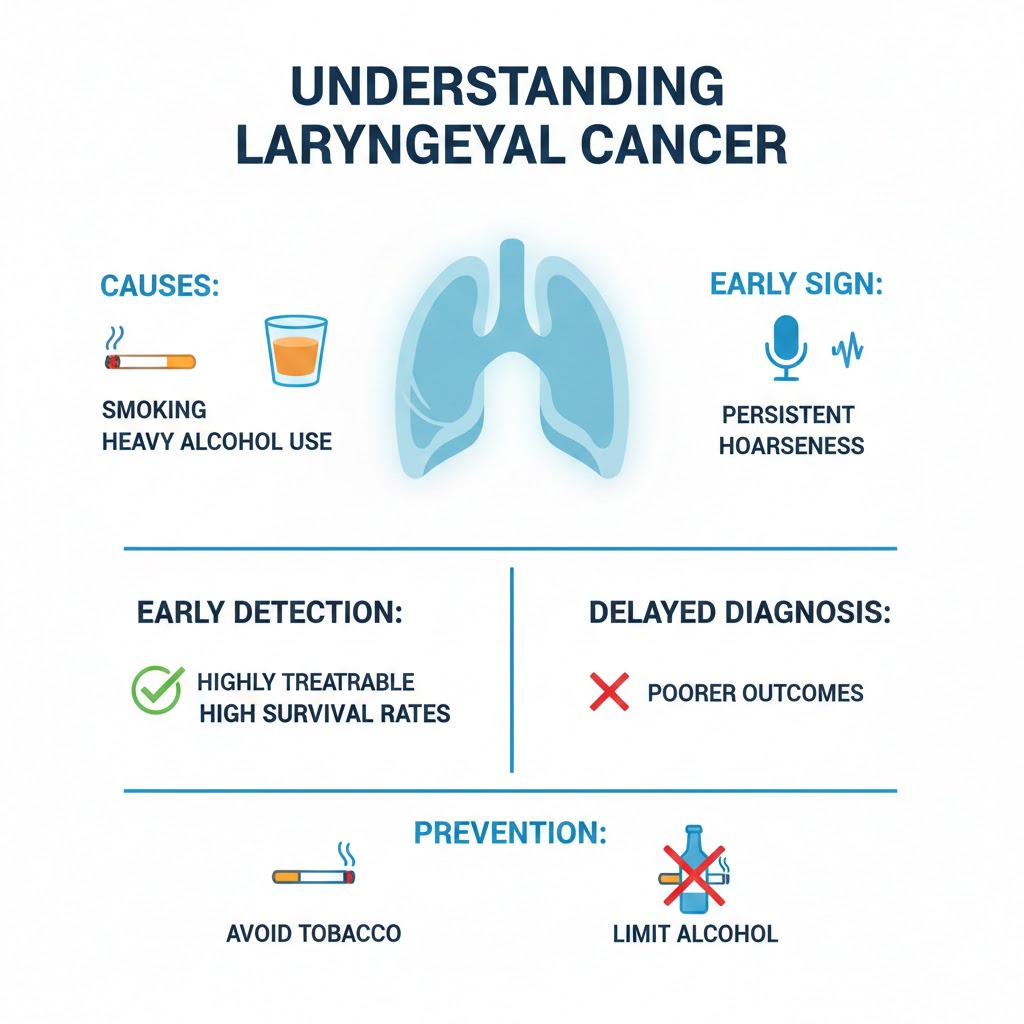
    Laryngeal cancer affects the voice box and is most often caused by smoking and heavy alcohol use. Persistent hoarseness is the most common early sign, along with throat discomfort or difficulty swallowing. When detected early, the disease is highly treatable and survival rates are high; outcomes are poorer when diagnosis is delayed. Prevention through avoiding tobacco and excessive alcohol, and prompt medical attention for lasting voice changes, are key to saving lives.

    Laryngeal cancer affects a vital organ: the larynx, often called the voice box. Located at the top of the windpipe, the larynx plays a central role in breathing, speaking, and swallowing. When cancer develops there, it can profoundly alter daily life, sometimes in ways that are both visible and audible.

    Laryngeal cancer is far more common in men than in women, a difference that largely reflects patterns of tobacco and alcohol use. The disease is usually diagnosed after the age of 50, though cases in younger people are not unheard of.

    The causes of laryngeal cancer are well established. Tobacco is by far the leading risk factor. Cigarettes, cigars, pipes, and even some smokeless tobacco products expose the lining of the larynx to carcinogenic substances that, over time, can trigger malignant changes. Alcohol acts as a powerful accomplice: heavy drinking combined with smoking multiplies the risk. Other factors can also play a role, including occupational exposure to certain chemicals, such as asbestos or wood dust. Infection with the human papillomavirus, better known for its link to cervical cancer, has also been implicated in a subset of cases.

    Because the main causes are known, prevention is straightforward. Avoiding tobacco dramatically reduces the risk, and the benefits begin soon after quitting. Limiting alcohol consumption adds further protection. Workplace safety measures that reduce exposure to harmful fumes and dusts matter as well.

    The first signs of the disease are often subtle, which explains why diagnosis can be delayed. Persistent hoarseness is the most common warning sign, especially when it lasts longer than a few weeks and has no obvious cause. A sore throat that does not go away, difficulty or pain when swallowing, a sensation of a lump in the throat, chronic cough, or ear pain can also be clues. In more advanced stages, breathing may become difficult, or a mass may be felt in the neck due to spread to nearby lymph nodes.

    When such symptoms raise suspicion, diagnosis usually begins with a careful examination of the throat by an ear, nose, and throat specialist. Using a small camera passed through the nose or mouth, the doctor can visualize the larynx directly. If an abnormal area is seen, a biopsy is required to confirm the presence of cancer. Imaging tests such as CT scans, MRI, or PET scans help determine how far the disease has spread, information that is crucial for choosing the best treatment.

    The course of laryngeal cancer varies widely. Tumors confined to the vocal cords tend to be detected earlier, because even small lesions can affect the voice. These early-stage cancers generally have an excellent prognosis. Cancers that arise above or below the vocal cords may grow larger before causing symptoms and are therefore more often diagnosed at a later stage. Over time, untreated cancer can invade nearby tissues or spread to lymph nodes and distant organs, making treatment more complex and outcomes less favorable.

    Treatment depends on the stage of the disease, the exact location of the tumor, and the patient’s overall health. For early cancers, radiation therapy or limited surgery can often eliminate the tumor while preserving the voice. More advanced cases may require a combination of surgery, radiotherapy, and chemotherapy. In some situations, part or all of the larynx must be removed to control the disease, a life-saving operation that has profound consequences for speech and breathing. Advances in reconstructive surgery, voice rehabilitation, and assistive technologies have greatly improved quality of life for people who undergo such procedures.

    Survival rates reflect this wide spectrum of disease. When laryngeal cancer is diagnosed at an early stage, five-year survival can exceed 80 or even 90 percent. For cancers detected later, especially those that have spread beyond the larynx, survival drops significantly, often to around 40 percent or less. These figures underscore a simple but crucial message: early detection saves lives.

    Laryngeal cancer is a disease in which prevention, awareness of symptoms, and timely medical attention make a tangible difference.


    Use the ‘Comments’ field below to share your experience with larynx cancer or to suggest improvements to this article.


  • Oral cancer and smoking

    Oral cancer and smoking

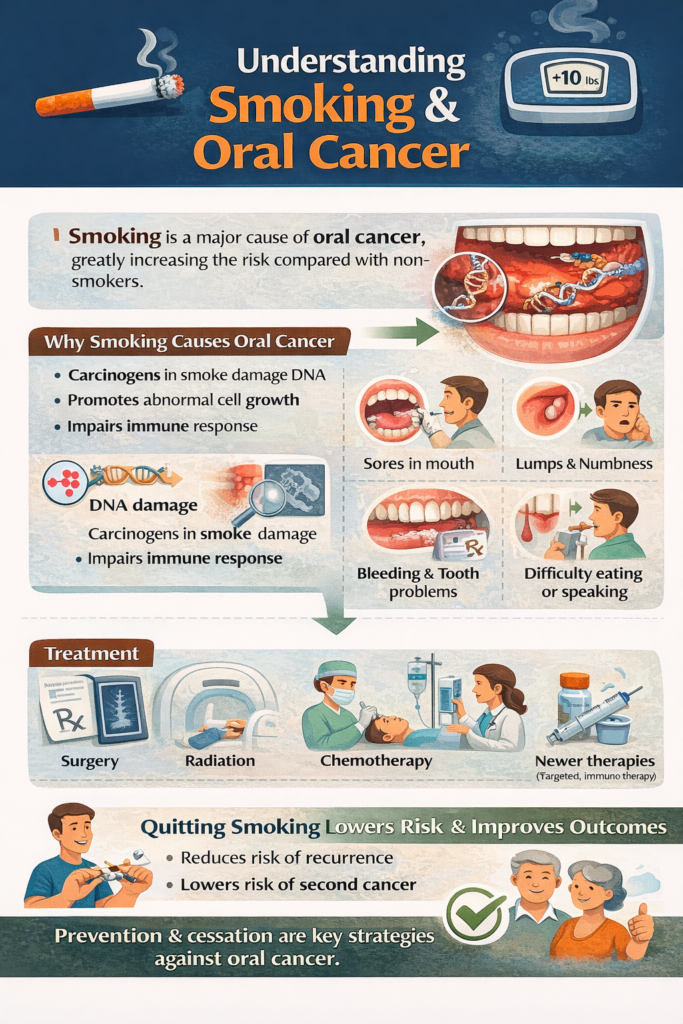
    Smoking is notorious for its role in lung cancer, but its impact on the mouth and throat is often underestimated. Cancer of the oral cavity, which includes the lips, tongue, gums, floor of the mouth, and palate, is a serious disease whose primary cause remains tobacco smoking

    Who is Affected:

    Tobacco use is by far the most significant risk factor for oral cancer. The risk for a person who smokes can be multiplied by five or more compared to someone who has never touched tobacco. This correlation applies not only to cigarettes but also to cigars and pipes.

    It is crucial to emphasize, however, that oral cancer is not exclusively a smoker’s disease. A significant percentage of cases occur in individuals who have never smoked. These cases are often linked to other risk factors, notably alcohol use and infection with the Human Papillomavirus (HPV). The combined effect of alcohol and tobacco is strongly synergistic, multiplying the risk exponentially.

    The Mechanism of the Disease

    The reason tobacco smoke triggers oral cancer lies in its chemical composition. Tobacco smoke contains thousands of chemical substances, dozens of which are known carcinogens. When these compounds come into contact with the delicate tissues of the mouth, they attack the DNA of the epithelial cells. These toxic substances cause genetic mutations which, over time and with repeated exposure, disrupt the normal mechanisms of cell growth and division. The mutated cells then begin to multiply uncontrollably, forming precancerous lesions, such as leukoplakia (white patch) or erythroplakia (red patch), which can progress to squamous cell carcinoma, the most common form of oral cancer. The chronic inflammation induced by tobacco only worsens this carcinogenic process.

    Signs, Diagnosis, and Treatment

    Oral cancer, if detected early, offers excellent chances of cure. The problem lies in the fact that the initial symptoms are often subtle or mistaken for benign conditions.

    The symptoms to watch out for are:

    • A sore or ulcer in the mouth or on the lip that does not heal after two weeks.
    • The appearance of a persistent white, red, or mixed patch on the oral lining or tongue.
    • A thickening, lump, or nodule in the cheek or neck.
    • Unexplained pain, numbness, or bleeding in the mouth.
    • Difficulty chewing, swallowing, or moving the tongue.

    The diagnosis begins with a thorough clinical examination, often performed by a dentist or physician. Any persistent suspicious lesion requires a biopsy, which involves taking a small sample of tissue for laboratory analysis. If cancer is confirmed, imaging tests (CT scan, MRI, PET scan) are performed to determine the extent of the tumor and to check whether it has reached the lymph nodes in the neck or other parts of the body, or whether the cancer has spread to other organs (metastasis).

    Treatment depends on the stage and location of the cancer. It most often involves a combination of:

    • Surgery to remove the tumor and, if necessary, the affected lymph nodes.
    • Radiation therapy to destroy remaining cancer cells.
    • Chemotherapy or immunotherapy in more advanced cases or to increase the effectiveness of other treatments.

    Prognosis and the Importance of Quitting

    The prognosis is directly related to the stage of the cancer at the time of diagnosis. When the disease is localized and detected very early, the five-year survival rate is significantly higher. Unfortunately, many cases are diagnosed at an advanced stage, when the cancer has spread to the lymph nodes, which makes treatment more arduous and significantly reduces the chances of recovery.

    The most powerful impact on the prognosis lies in the immediate and definitive cessation of tobacco use, even after diagnosis. Quitting smoking not only reduces the risk of recurrence but also improves the response to treatments and the overall quality of life of the patient. Prevention remains the most effective weapon: avoiding tobacco and excessive alcohol use are the fundamental steps to guard against this devastating disease.


    Use the ‘Comments’ field below to share your experience with oral cancer or to suggest improvements to this article.


  • Oral health and smoking

    Oral health and smoking

    Smoking has direct and devastating effects on the mouth, starting with colored teeth and bad breath, progressing to tooth decay, and potentially leading to cancer.

    Why Smoking and Oral Disease Are Linked

    The link between smoking and oral health problems stems from the thousands of toxic chemicals found in tobacco smoke. When these chemicals enter the mouth, they disrupt its natural defenses and processes. Nicotine, carbon monoxide, tar, and various carcinogens in cigarettes irritate soft tissues, impair blood circulation, weaken the immune system, and promote the proliferation of harmful bacteria.

    Smoking restricts the flow of oxygen and nutrients to the gums and bone, impairing the mouth’s ability to heal and fight off infections. It also changes the composition of saliva, making it less effective at neutralizing acids and washing away food particles and bacteria. This combination of factors creates a hostile environment where oral diseases can flourish, often with greater severity and resistance to treatment.

    Dental Problems: Beyond the Stain

    The most visible sign of a smoker’s habit is often the yellowish or brownish stains on their teeth, a direct result of tar accumulating on the enamel. However, the damage goes far deeper than aesthetics. Smoking significantly increases the risk of dental caries, or cavities. The altered oral environment, with reduced saliva flow and a shift towards more acid-producing bacteria, creates ideal conditions for tooth decay.

    Furthermore, smokers are at a much higher risk for oral cancer. The carcinogens in tobacco smoke directly damage the cells lining the mouth, tongue, lips, throat, and salivary glands, leading to abnormal cell growth. These cancers often present as persistent sores, lumps, or white/red patches that don’t heal, and early detection is critical for survival.

    Periodontal Problems: The Foundation Crumbles

    Perhaps one of the most insidious effects of smoking is its impact on periodontal health, which refers to the gums and the bone supporting the teeth. Smokers are at a significantly elevated risk for gingivitis (inflammation of the gums) and, more severely, periodontitis.

    Smoking masks the classic signs of gum disease. Nicotine constricts blood vessels, meaning smokers often experience less bleeding gums, even when severe inflammation is present. This can lull them into a false sense of security, delaying diagnosis and treatment until the disease has advanced. By the time it’s noticeable, the damage can be extensive.

    Periodontitis in smokers progresses more rapidly and is often more severe than in non-smokers. It leads to the destruction of the bone and connective tissues that hold teeth in place, eventually resulting in loose teeth and, ultimately, tooth loss. Smokers also respond less favorably to periodontal treatments and are more prone to recurrence of the disease.

    Bad Breath: A Lingering Consequence

    Halitosis, commonly known as bad breath, is another prevalent issue among smokers. The lingering smell of stale tobacco smoke itself is a primary contributor. However, the problem is compounded by the drying effect of smoke on the mouth, leading to reduced saliva flow and an increase in odor-producing bacteria. Periodontal disease, also exacerbated by smoking, further contributes to halitosis, as decaying tissue and bacterial buildup release unpleasant sulfur compounds.

    Diminished Senses of Taste and Smell: A Muted World

    Smoking dulls the senses of taste and smell. The chemicals in tobacco smoke can damage the taste buds and interfere with the olfactory receptors in the nose. Smokers often report that food tastes bland or that they struggle to discern subtle flavors. This reduced sensory perception can diminish the enjoyment of eating and drinking, and for some, it even contributes to unhealthy dietary choices as they seek stronger-tasting foods.

    Dry Mouth: A Gateway to Further Issues

    Xerostomia, or dry mouth, is a common complaint among smokers. The heat and chemicals in cigarette smoke irritate the salivary glands and can reduce saliva production. Saliva is crucial for oral health; it washes away food particles, neutralizes acids, helps remineralize tooth enamel, and contains antimicrobial agents. A chronically dry mouth leaves individuals more susceptible to cavities, gum disease, fungal infections (like thrush), and difficulty speaking or swallowing.

    Safeguarding Your Smile: Oral Hygiene Advice

    The most impactful advice for anyone concerned about their oral health and smoking is unequivocal: quit smoking. Cessation immediately begins to reverse many of the damaging effects and significantly reduces the risk of developing further complications.

    Beyond quitting, meticulous oral hygiene practices are essential for smokers and former smokers:

    • Brush thoroughly twice a day: Use a soft-bristled brush and fluoride toothpaste to gently clean all tooth surfaces and along the gumline.
    • Floss daily: Flossing removes plaque and food particles from between teeth and under the gumline, areas a toothbrush cannot reach.
    • Regular dental check-ups and cleanings: Visit your dentist at least twice a year, or more frequently if advised, for professional cleanings and examinations. Your dentist can monitor for early signs of oral cancer, gum disease, and other problems.
    • Use an antimicrobial mouthwash: A therapeutic mouthwash can help reduce bacteria in the mouth.
    • Stay hydrated: Drinking plenty of water helps combat dry mouth and encourages saliva production.
    • Maintain a balanced diet: Limit sugary and acidic foods and drinks that can contribute to tooth decay.
    • Be vigilant for changes: Any persistent sore, lump, patch, or unusual bleeding in your mouth should be reported to your dentist immediately.

    Use the ‘Comments’ field below to share your experience or to suggest improvements to this article.


  • Buerger’s disease

    Buerger’s disease

    While smoking carries countless risks, few are as uniquely and inextricably linked to tobacco use as Buerger’s disease, or thromboangiitis obliterans. This rare and devastating condition strikes at the arteries and veins that carry blood to the extremities, often leading to chronic pain, severe tissue damage, and amputation.

    A Disease of Occlusion: What is Buerger’s Disease?

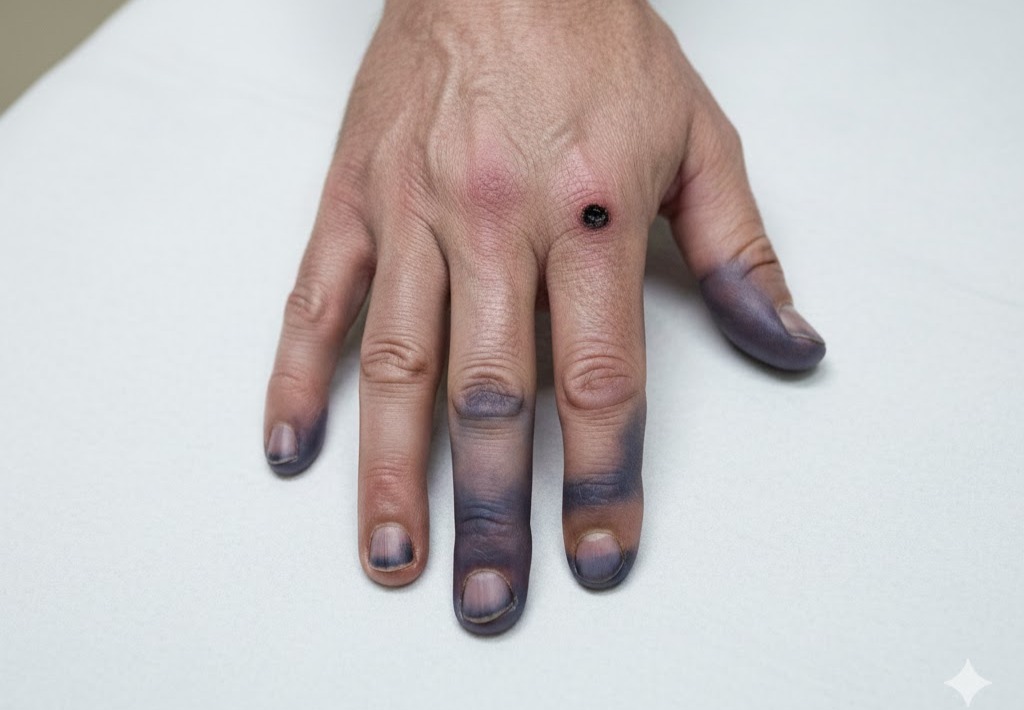
    Buerger’s disease is a non-atherosclerotic, segmental, inflammatory condition that primarily affects the small and medium-sized blood vessels in the arms and hands and, most commonly, the legs. Unlike other vascular diseases related to fatty plaques, Buerger’s involves an inflammatory process that causes blood vessels to swell. This swelling eventually leads to the formation of blood clots, or thrombi, which completely or partially block the flow of blood. This occlusion prevents oxygen and nutrients from reaching the tissues, a state known as ischemia.

    The disease typically manifests first in the hands and feet, particularly in the fingers and toes. Early symptoms often include Raynaud’s phenomenon, where the fingers or toes turn white, then blue, and finally red upon exposure to cold or stress. As the condition evolves, patients experience a deep, burning pain, often described as throbbing, in the affected limbs. This pain is particularly severe even when the limb is at rest, distinguishing it from claudication (pain during exercise). As the blood supply diminishes further, the skin may appear thin, shiny, and pale, and the pulses in the distal extremities become weak or absent.

    Progression and Complications

    The natural evolution of Buerger’s disease, if the cause is not eliminated, is grim. The persistent lack of blood flow eventually leads to ulceration and tissue death (gangrene). These ulcers are excruciatingly painful and difficult to heal due to the poor circulation. Once gangrene sets in, the tissue is irreversibly damaged, often turning black and necrotic.

    The untreated or unaddressed progression of Buerger’s disease makes amputation a common and tragic outcome. The disease tends to advance segmentally, meaning an initial amputation may be followed by the loss of the limb above the joint (for example, the loss of the foot followed by the loss of the lower leg) as the disease climbs the vascular tree. It is a relapsing and remitting condition, meaning periods of remission can be followed by sudden, painful flares that require aggressive medical intervention.

    Tobacco’s Irrefutable Causal Role

    The connection between Buerger’s disease and tobacco is not merely correlational; it is causal. Nearly all patients diagnosed with this condition are active users of tobacco. The substances in tobacco appear to trigger a unique inflammatory and autoimmune reaction in genetically susceptible individuals, leading to the destruction of the blood vessel walls.

    Critically, cessation is the only definitive treatment. There are no surgical or pharmacological cures for Buerger’s disease; all other medical interventions are only supportive or aimed at managing symptoms.

    Nicotine Itself: Nicotine is the addictive component in tobacco, and it is a vasoconstrictor (it narrows blood vessels). While this vasoconstriction is certainly undesirable for someone with a vascular disease, there is no substantial evidence to suggest that nicotine alone, when administered in non-combustible forms (like patches, gums), initiates or sustains the inflammatory-occlusive process that defines Buerger’s disease. One case of a vaper of nicotine e-liquid who had smoked very little in the past has nevertheless been reported.

    Treatment and the Absolute Necessity of Quitting Smoking

    The management of Buerger’s disease is first and foremost about immediate and permanent cessation of all tobacco and nicotine use. Anything less guarantees the progression of the disease and the eventual loss of limbs.

    Medical treatments focus on relieving pain and improving blood flow:

    • Vasodilators: Medications can be used to try and widen the remaining healthy blood vessels.
    • Pain Management: Due to the severity of the pain, strong analgesics are often required.
    • Wound Care: Aggressive treatment of ulcers and infections is necessary to prevent the spread of gangrene.
    • Sympathectomy: In some cases, a surgical procedure to cut nerves controlling vascular tone can be performed to attempt to increase blood flow, though its long-term efficacy is debated.

    Nicotine Replacement Therapy: A Necessary Caveat

    Given the absolute importance of quitting, the role of nicotine replacement therapy (NRT) in Buerger’s patients is a complex topic. Since nicotine itself is a vasoconstrictor, meaning it causes blood vessels to narrow, there is a theoretical concern that NRT could aggravate the underlying vascular constriction inherent in Buerger’s disease.

    However, clinical consensus leans toward the understanding that the thousands of other toxins and combustion products in tobacco smoke are vastly more dangerous than medicinal nicotine alone. For patients with Buerger’s disease, the urgency of eliminating smoke exposure outweighs the theoretical risk of pure nicotine. Therefore, NRT is often cautiously used under strict medical supervision to aid cessation, but only as a short-term bridge to complete abstinence. NRT is considered a safer, temporary option compared to the lethal certainty of continued smoking. The message remains uncompromising: quitting completely and permanently is the patient’s only hope for saving their limbs and halting the disease’s deadly march. The temporary use of NRT is deemed acceptable to help achieve the ultimate goal: zero exposure to tobacco.


    Reference:

    Memon N, et al. Progression of Buerger’s Disease in the Absence of Conventional Tobacco Exposure: A Case of Vape Associated Disease. J Dermatol Res. 2025;6(2):1-3. https://doi.org/10.46889/JDR.2025.6205


    Use the ‘Comments’ field below to share your experience with Buerger’s disease or to suggest improvement to this page.


  • Sexuality and smoking

    Sexuality and smoking

    Smoking is best known for damaging the heart and lungs, but it also affects your sex life, your ability to have children and your intimate health. The encouraging part is that many of these effects improve after you quit, often sooner than people expect.

    By Jean-François Etter, professor of public health.

    Why smoking affects sexual arousal

    Sexual arousal depends on healthy blood flow. Cigarette smoke contains thousands of chemicals that injure the lining of blood vessels, make them narrower and stiffer, and over time contribute to atherosclerosis (hardening and blockage of the arteries). Nicotine also causes blood vessels to constrict with every cigarette.

    For men, an erection requires a rapid increase in blood flow. Studies consistently find that smokers are around 1.5 times more likely to develop erectile dysfunction (ED) than non-smokers, and the risk rises with the number of cigarettes smoked and the number of years of smoking. ED in smokers also tends to appear at a younger age.

    A warning : because the arteries supplying the penis are small, ED can be one of the first signs of wider blood-vessel disease. If you smoke and notice erection problems, see a doctor. It may be an early signal about your heart health, and it is a good reason to quit.

    For women, reduced blood flow to the genital area can mean weaker arousal, less natural lubrication and more difficulty reaching orgasm. This can make sex less enjoyable or uncomfortable. Research in this area is less extensive than for ED, but the underlying mechanism is the same, and the size of the effect is also the same : the risk of female sexual dysfunction is increased 1.5 times in smokers.

    Smoking and your intimate health

    Smoking weakens several of the body’s defences. One well-established example is HPV, the virus behind most cervical cancers. Smokers are more likely to be infected than non-smokers, and smokers who are infected are more likely to have the infection persist and to develop precancerous changes in the cervix and carcinoma of the cervix. Smoking is also a risk factor for bacterial vaginosis.Smoking can also slow healing, which may matter after infections or surgical procedures.
    HPV vaccination, regular screening and quitting smoking together offer the best protection.

    Smoking and fertility

    Smoking can make it harder to conceive, for men and women alike.

    • Sperm: Smoking is linked to lower sperm concentration, poorer movement (motility) and more abnormally shaped sperm, reducing the chances of fertilisation.
    • Eggs and hormones: In women, smoking can disrupt the menstrual cycle, damage eggs and bring on menopause one to four years earlier on average.
    • Conception and pregnancy: Smokers generally take longer to conceive and have a higher risk of miscarriage and ectopic pregnancy. See our article on smoking and pregnancy for more.
    • Fertility treatment: Smoking lowers the success rates of IVF and other assisted reproduction.
    • Secondhand smoke: A non-smoking partner exposed to smoke is also affected, and exposure during pregnancy harms the baby.

    If you use hormonal contraception, note that combining it with smoking carries specific risks, especially blood clots. Read more about smoking and the contraceptive pill.

    Other effects on intimacy

    Smoking can reduce stamina and cause breathlessness, which affects physical activity of every kind. The smell of smoke on breath, hair and clothes, along with skin ageing and stained teeth, can also affect how comfortable people feel about their bodies and closeness with others. These effects vary from person to person, and many people notice them more in themselves than their partners do.

    What happens when you quit?

    The body begins to repair itself sooner than most people think.

    • Within weeks: circulation starts to improve and breathing becomes easier.
    • Within about three months: sperm quality can begin to recover.
    • Within months: many former smokers, especially younger men and those with milder problems, notice improvement in erectile function.
    • Over the longer term: fertility, pregnancy outcomes and cardiovascular risk improve, with the benefits growing the longer you stay smoke-free.

    Recovery is not guaranteed for everyone, particularly after many years of smoking, but quitting offers the best chance of improvement. It also helps any other treatment work better.

    The next steps

    • Speak with a doctor about any sexual or fertility concerns. Several causes are possible, and effective treatments exist.
    • If you are trying to conceive, quitting smoking now, for both partners, improves your chances.
    • Support makes quitting much more likely to succeed. Nicotine replacement therapy and prescription medications can double your chances compared with going it alone, and your doctor or pharmacist can support you and help you choose the best treatment. Or you can call a helpline.

    This article is for general information and is not a substitute for medical advice.


    Please use the Comments field below to share your experience or to suggest improvements to this article.


    Rate this article by clicking on the desired number of stars:
    (No Ratings Yet)


    References:

    Salari, N., Hasheminezhad, R., Abdolmaleki, A. et al. The effects of smoking on female sexual dysfunction: a systematic review and meta-analysis. Arch Womens Ment Health 25, 1021–1027 (2022). https://doi.org/10.1007/s00737-022-01281-1

    Mark S. Allen, Emma E. Walter, Health-Related Lifestyle Factors and Sexual Dysfunction: A Meta-Analysis of Population-Based Research, The Journal of Sexual Medicine, Volume 15, Issue 4, April 2018, Pages 458–475, https://doi.org/10.1016/j.jsxm.2018.02.008

    Kovac, J. R., Khanna, A., & Lipshultz, L. I. (2015). The effects of cigarette smoking on male fertility. Postgraduate Medicine, 127(3), 338–341. https://doi.org/10.1080/00325481.2015.1015928

    Alan Penzias, et al., Smoking and infertility: a committee opinion, Fertility and Sterility, Volume 110, Issue 4, 2018, Pages 611-618, ISSN 0015-0282, https://doi.org/10.1016/j.fertnstert.2018.06.016.

    Smart S, Singal A, Mindel A. Social and sexual risk factors for bacterial vaginosis. Sexually Transmitted Infections 2004;80:58-62. https://doi.org/10.1136/sti.2003.004978

    Cao S, Yin X, Wang Y, Zhou H, Song F, et al. (2013) Smoking and Risk of Erectile Dysfunction: Systematic Review of Observational Studies with Meta-Analysis. PLOS ONE 8(4): e60443. https://doi.org/10.1371/journal.pone.0060443

    Salari, N., Hasheminezhad, R., Abdolmaleki, A. et al. The effects of smoking on female sexual dysfunction: a systematic review and meta-analysis. Arch Womens Ment Health 25, 1021–1027 (2022). https://doi.org/10.1007/s00737-022-01281-1

    Salvatore Vaccarella, Rolando Herrero, Peter J F Snijders, Min Dai, Jaiye O Thomas, Nguyen Trong Hieu, Catterina Ferreccio, Elena Matos, Hector Posso, Silvia de Sanjosé, Hai Rim Shin, Sukhon Sukvirach, Eduardo Lazcano-Ponce, Nubia Muñoz, Chris J L M Meijer, Silvia Franceschi, the IARC HPV Prevalence Surveys (IHPS) Study Group, Smoking and human papillomavirus infection: pooled analysis of the International Agency for Research on Cancer HPV Prevalence Surveys, International Journal of Epidemiology, Volume 37, Issue 3, June 2008, Pages 536–546, https://doi.org/10.1093/ije/dyn033

    Mzarico E, Gómez-Roig MD, Guirado L, Lorente N, Gonzalez-Bosquet E. Relationship between smoking, HPV infection, and risk of Cervical cancer. Eur J Gynaecol Oncol. 2015;36(6):677-80. PMID: 26775350.

    Kovac JR, Khanna A, Lipshultz LI. The effects of cigarette smoking on male fertility. Postgrad Med. 2015 Apr;127(3):338-41. Epub 2015 Feb 19. https://doi.org/10.1080/00325481.2015.1015928.

    Harte, C.B. and Meston, C.M. (2012), Association between smoking cessation and sexual health in men. BJU International, 109: 888-896. https://doi.org/10.1111/j.1464-410X.2011.10503.x

    A.L. Waylen, M. Metwally, G.L. Jones, A.J. Wilkinson, W.L. Ledger, Effects of cigarette smoking upon clinical outcomes of assisted reproduction: a meta-analysis, Human Reproduction Update, Volume 15, Issue 1, January-February 2009, Pages 31–44, https://doi.org/10.1093/humupd/dmn046

    Sven Cnattingius, The epidemiology of smoking during pregnancy: Smoking prevalence, maternal characteristics, and pregnancy outcomes, Nicotine & Tobacco Research, Volume 6, Issue Suppl_2, April 2004, Pages S125–S140, https://doi.org/10.1080/14622200410001669187


  • Women’s health and smoking

    Women’s health and smoking

    In this section, you will find information on the specific health issues faced by women who smoke:


  • Mental health and smoking

    Mental health and smoking


    Smoking remains one of the main causes of ill health in people with mental disorders, yet it is still too often treated as a side issue in mental health care. While smoking rates in the general population have fallen steadily over recent decades, they remain stubbornly high among people with mental illness. This gap has become one of the main reasons why people with mental disorders die earlier than the rest of the population.

    Across many countries, people with depression, anxiety disorders, bipolar disorder, schizophrenia and other severe mental illnesses are far more likely to smoke than those without these conditions. In psychiatric inpatient settings, smoking has historically been part of the culture, sometimes tolerated or even facilitated. As a result, tobacco use has become normalised in mental health services in a way that would now be unthinkable in most other areas of healthcare.

    The consequences are profound. The excess deaths seen in people with serious mental illness are not primarily due to suicide or the psychiatric conditions themselves, but to heart disease, cancer and respiratory illness. Smoking is a major driver of all three. In effect, tobacco is responsible for a large proportion of the lost years of life experienced by people with mental disorders. Addressing smoking is therefore not a peripheral issue but central to improving both longevity and quality of life in this population.

    One reason progress has been slow is the persistence of damaging myths. Perhaps the most enduring is the belief that people with mental illness cannot or do not want to quit smoking. This assumption has shaped clinical practice for decades and has led many healthcare professionals to avoid raising the issue altogether. Yet the evidence tells a very different story. Many people with mental disorders want to stop smoking, make repeated quit attempts and are just as motivated as other smokers. When offered appropriate support, they can and do quit successfully.

    Another common fear is that stopping smoking will worsen psychiatric symptoms. This concern has been reinforced by the short-term irritability, depression, anxiety and sleep disturbance that can accompany nicotine withdrawal. However, large studies and systematic reviews show that, once withdrawal has passed, people who stop smoking tend to experience improvements in mood, anxiety and overall wellbeing. These benefits are seen in people with and without diagnosed mental disorders.

    Effective treatments for smoking cessation are available and work well for people with mental illness. Nicotine replacement therapy, bupropion and varenicline have all been shown to increase quit rates in this group. For many patients with mental disorders, nicotine dependence is high, and standard doses of nicotine replacement are often insufficient. Combination treatment, using a nicotine patch to provide a steady background level together with faster-acting products (gum, lozenge, spray) for cravings, is frequently needed. Some highly dependent smokers require higher-dose or longer courses of nicotine replacement than those typically offered in primary care, and this can be done safely with appropriate clinical oversight.

    What does require particular attention is the interaction between smoking and certain psychiatric medications. Tobacco smoke affects liver enzymes that break down drugs such as clozapine and olanzapine. When a patient stops smoking, blood levels of these medications can rise significantly, increasing the risk of side effects unless doses are adjusted. This is not a reason to discourage quitting, but it does mean that clinicians need to anticipate changes, monitor patients closely and modify doses where necessary. With planning and communication, these adjustments can be managed safely.

    Changing outcomes for patients will also require a shift in professional attitudes. Too many mental health clinicians still see smoking as a lesser evil or as a coping mechanism that should be left untouched. Training is essential to build confidence in delivering smoking cessation support and in managing nicotine withdrawal and medication interactions. When smoking status is routinely assessed, discussed and treated as part of standard care, quit attempts become more frequent and more successful.

    Service provision matters as well. People with mental disorders benefit from access to specialist smoking cessation services that understand the complexities of mental illness and can offer flexible, intensive support. Funding for these services is often inadequate, despite strong evidence that they are cost-effective and can dramatically reduce long-term healthcare costs. Integrating smoking cessation into mental health services, rather than referring patients elsewhere, increases engagement and reduces inequalities in access to care.

    Smokefree policies in mental health facilities have an important role to play. When introduced thoughtfully, alongside ready access to nicotine replacement and staff support, these policies can reduce smoking without worsening mental health or increasing aggression. They also send a clear message that the physical health of people with mental illness matters just as much as their mental health.

    Finally, there is a need for greater public and political awareness. Smoking among people with mental disorders has received far less attention than other health inequalities, despite its enormous impact. Policymakers, commissioners and service leaders need to recognise tobacco dependence as a treatable condition and a major driver of premature mortality in this population. Public discussion can help dismantle the stigma and low expectations that have allowed this problem to persist.

    Reducing smoking among people with mental illness is one of the most effective ways to improve both mental and physical health outcomes. The tools already exist. What is required now is the will to use them consistently, compassionately and at scale.


    Use the Comments field below to share your experience or to suggest improvements to this article.